The Respiratory System
Every cell in your body burns oxygen to make energy. Every one of them also makes carbon dioxide as waste. So 12 to 16 times a minute, your body trades one gas for the other. You never even have to think about it. This chapter follows a breath from the nostril to the tiny air sac where the trade happens. Then it explains the physics that pulls air in. It shows how the gases swap places and how clever chemistry carries them through the blood. Last, it covers the air volumes doctors measure to tell a healthy lung from a sick one. By the end, you will know not just how you breathe but why this whole elegant machine works the way it does.
By the end of this chapter you can
- Trace the path of air through the conducting and respiratory zones. Name each part it passes.
- Describe how the airway warms, humidifies, and filters the air you breathe in. Explain the mucociliary escalator.
- Draw the respiratory membrane. Explain why being thin and having a huge surface make it ideal for gas exchange.
- Explain the job of surfactant. Predict what happens when it is missing.
- Use Boyle’s law to explain breathing in and breathing out. Name the muscles and pressures involved in each.
- Apply partial-pressure gradients to external and internal respiration. Say which way each gas moves and why.
- Describe how oxygen and carbon dioxide are carried in the blood. Include hemoglobin and the bicarbonate system.
- Define the lung volumes and capacities. Explain how spirometry tells obstructive disease from restrictive disease.
Section 1The respiratory tract
Two zones: a highway and a destination
The respiratory system has one main job. It moves oxygen in and carbon dioxide out. But it does more, too. It warms and moistens the air and filters out dirt. It gives you your sense of smell and makes your voice. It also helps control the pH of your blood, meaning how acidic it is.
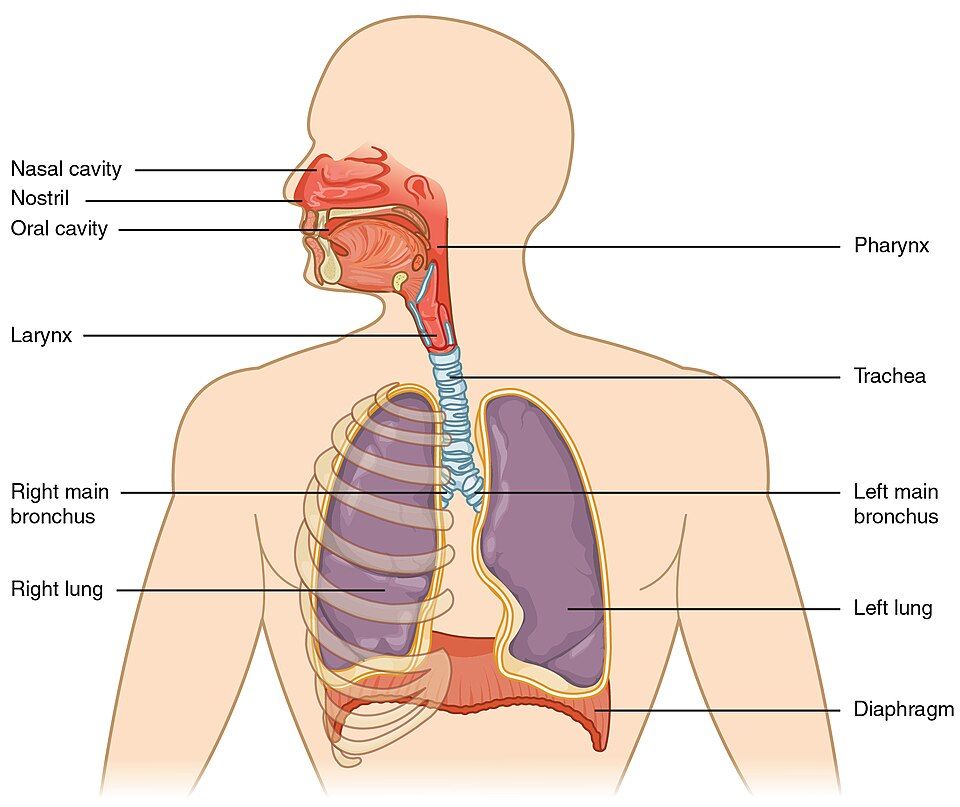
To do all this, the airway is split into two working zones. The conducting zone is the plumbing. It is made of the nose, pharynx, larynx, trachea, bronchi, and bronchioles. These tubes carry air, but they never trade gases. The respiratory zone is where oxygen is actually traded for carbon dioxide. It is made of the respiratory bronchioles, alveolar ducts, and alveoli. Think of the conducting zone as the highway and the respiratory zone as the destination. Air only does its real work once it arrives.
Doctors also divide the tract by location. The upper respiratory tract is everything above the larynx. That means the nose, nasal cavity, sinuses, and pharynx. The lower respiratory tract is the larynx and everything below it. That means the trachea, bronchi, and lungs. This is why a "cold" feels so different from bronchitis or pneumonia. A cold is an upper-tract infection. The other two are lower-tract problems.
The journey of a breath
Follow one breath in. Air enters the nostrils and swirls through the nasal cavity. It passes into the pharynx, or throat, which has three parts. Next it slips through the larynx, the voice box. A flap called the epiglottis guards the larynx. It flips down when you swallow, so food goes to the esophagus and not the lungs.
Then air enters the trachea, or windpipe. C-shaped rings of cartilage hold it open at all times. The trachea splits into the right and left primary bronchi. These branch again and again, like an upside-down tree. They form smaller and smaller bronchi and then bronchioles. At last the tubes end in clusters of alveoli, the tiny air sacs. The whole branching pattern is called the bronchial tree.
| Structure | Zone | Key feature |
|---|---|---|
| Nasal cavity | Conducting | Warms, moistens, and filters air; lined with mucous membrane |
| Pharynx | Conducting | Shared path for air and food (naso-, oro-, laryngo-) |
| Larynx | Conducting | Voice box; the epiglottis guards the airway |
| Trachea | Conducting | C-shaped cartilage rings keep it open |
| Bronchi | Conducting | Branch into each lung, then into lobes and segments |
| Bronchioles | Conducting | No cartilage; smooth muscle sets how wide they are |
| Alveoli | Respiratory | Thin-walled air sacs where gas exchange happens |
The air that arrives is conditioned
By the time air reaches the alveoli, it has changed a lot. It has been warmed to body heat. It is full of water vapor, and it has been scrubbed almost clean. The nasal cavity does most of this work. Its rich blood supply gives off heat. Its mucous lining traps dust and germs.
Under that mucus sits a carpet of tiny hairs called cilia. They beat in waves toward the throat. This is the mucociliary escalator. Like a moving stairway, it sweeps trapped dirt up and out. Then you swallow it or cough it away. This tireless cleaning system protects the delicate air sacs from the outside world.
Walk the whole tract, one part at a time, in the interactive below.
- The conducting zone (nose → bronchioles) moves air. The respiratory zone (respiratory bronchioles → alveoli) trades gases.
- Air path: nose → pharynx → larynx → trachea → bronchi → bronchioles → alveoli.
- Air coming in is warmed, humidified, and filtered. The mucociliary escalator sweeps dirt up and out.
Section 2The alveolus & respiratory membrane
A surface the size of a room
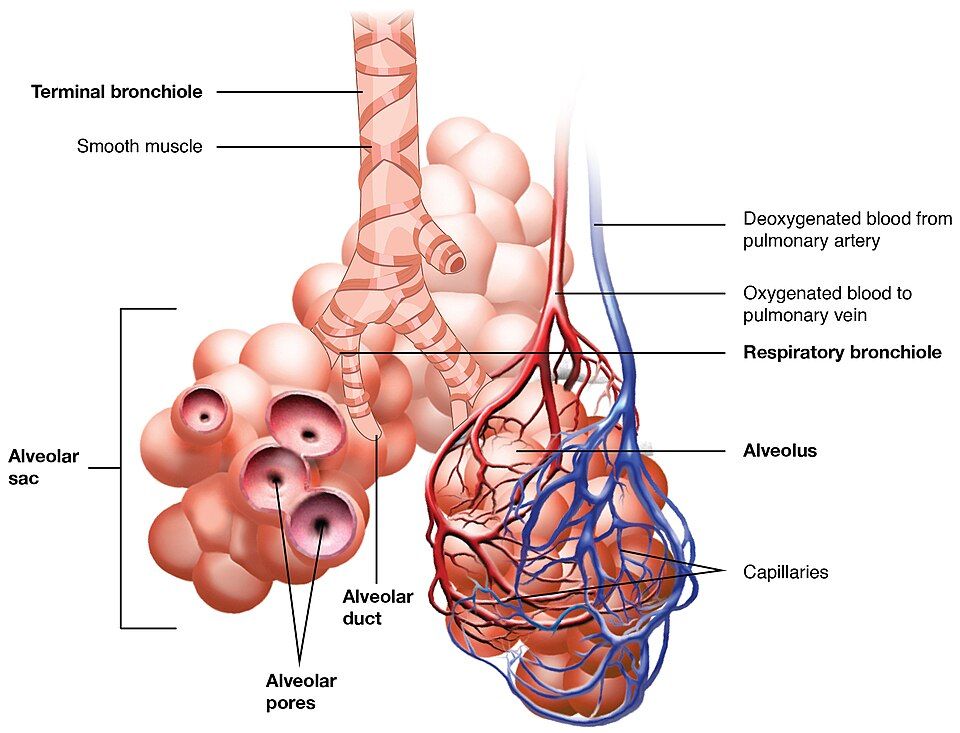
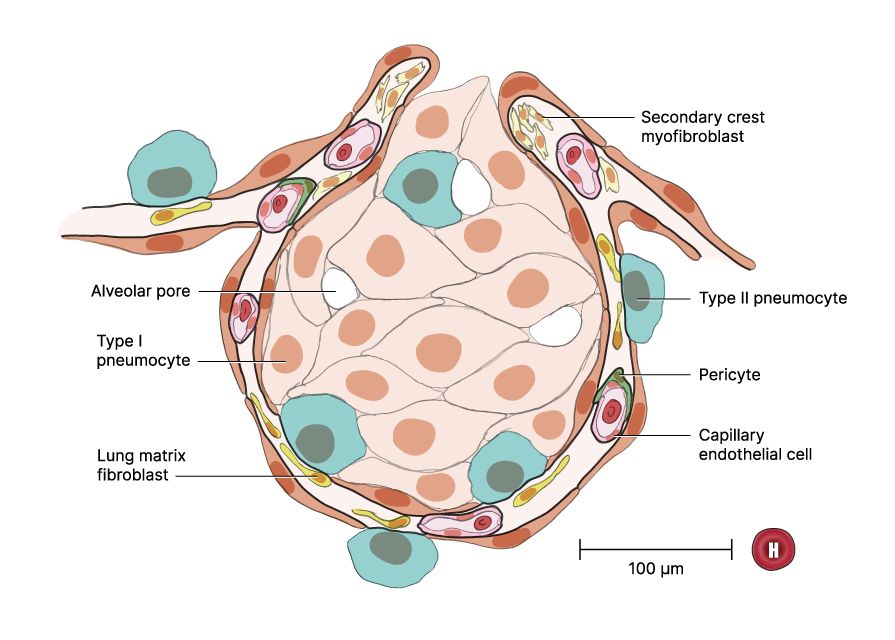
Your lungs hold about 300 million alveoli. Each is a hollow sac, like a bubble, wrapped in a mesh of capillaries. One alone is tiny. But spread out, all their walls would cover about 70 square meters. That is about the floor of a small apartment, packed inside your chest.
This huge area is the whole point. The more surface you spread out, the more gas can cross it at once. Structure fits function. Here, the function is to move oxygen and carbon dioxide as fast and in as large amounts as possible.
The respiratory membrane: three thin layers
Gases are traded across the respiratory membrane. This is the barrier between the air in the alveoli and the blood in the capillaries. It has an important-sounding name, but it is almost nothing at all. It is about 0.5 micrometers thick, which is thinner than a soap bubble.
It has just three layers. First is the alveolar wall, a single flat layer of type I cells. Last is the capillary wall, a single flat layer of cells that line the vessel. Between them are their fused basement membranes, glued together. Oxygen crosses all three and enters the blood in a split second. Carbon dioxide crosses the other way just as fast.
| Cell / layer | What it is | Job |
|---|---|---|
| Type I alveolar cell | Simple squamous (flat) cell | Makes up most of the wall; thin enough for gases to cross |
| Type II alveolar cell | Rounded cell scattered in the wall | Makes and releases surfactant |
| Alveolar macrophage | Roaming immune cell ("dust cell") | Swallows dirt and germs that reach the sac |
| Capillary endothelium | Flat cells lining the capillary | The blood side of the respiratory membrane |
Why does being thin matter so much? Gases cross much more slowly when the barrier gets thicker. Some diseases thicken this membrane. In pulmonary edema, fluid floods it. In pulmonary fibrosis, scar tissue stiffens it. Now oxygen has farther to travel. The patient gets short of breath, even though the air and the blood are both right there.
Surfactant: keeping the sacs from collapsing
A bubble with wet walls tends to collapse. That is because the water molecules lining it pull toward each other. This pull is called surface tension. If nothing stopped it, the smallest alveoli would snap shut every time you breathed out.
To prevent this, the type II alveolar cells release surfactant. It is a soapy mix of fats and proteins that coats the inside of the sacs. It breaks up the water’s pull and lowers surface tension. This keeps the sacs open and easy to fill.
Zoom into a single sac and its capillary in the interactive below.
- About 300 million alveoli give about 70 m² of surface for gas exchange.
- The respiratory membrane is about 0.5 µm thick. It has three layers: the alveolar wall, the fused basement membranes, and the capillary wall.
- Type II cells make surfactant. It lowers surface tension and keeps alveoli from collapsing.
Section 3Breathing mechanics
You make room, and air follows (Boyle’s law)
Here is a surprise. You do not actively suck air into your lungs. You make your chest bigger, and air rushes in on its own to fill the extra space.
The physics behind this is Boyle’s law. At a steady temperature, a gas’s pressure goes up when its volume goes down. Its pressure goes down when its volume goes up. Squeeze a container, and the pressure inside climbs. Make it bigger, and the pressure drops. Air always flows from higher pressure to lower pressure. So your muscles only have to change the size of your chest. The pressure difference moves the air for you.
Inspiration: an active pull
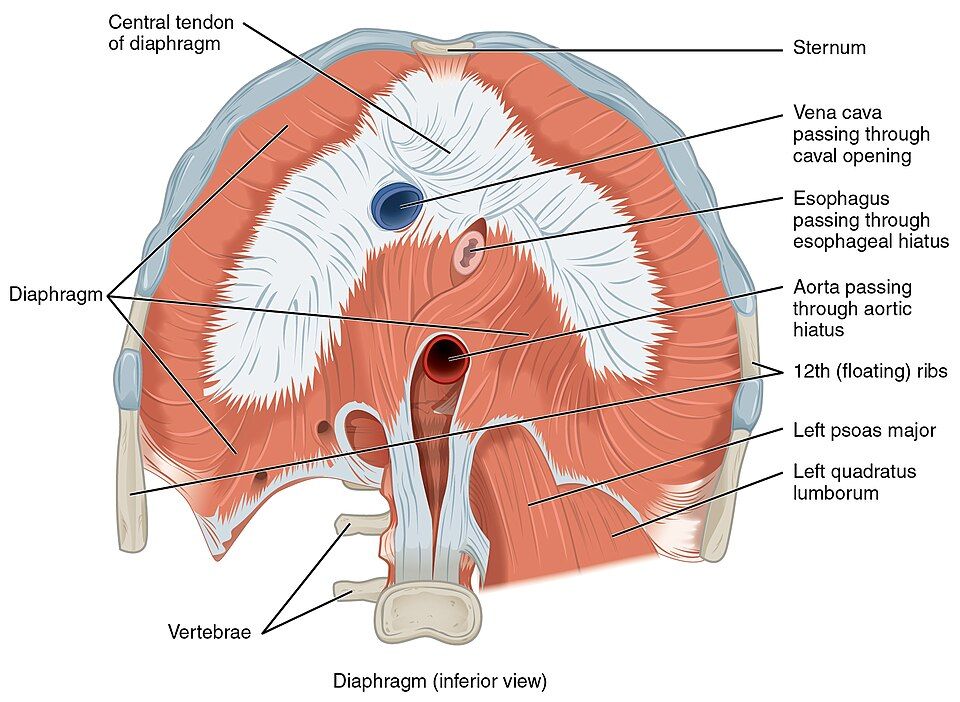
Breathing in, or inspiration, is active. It takes muscle work. The diaphragm is a dome of muscle under the lungs. It tightens and flattens downward. At the same time, the external intercostal muscles between the ribs lift the ribs up and out. Both actions enlarge the thoracic cavity, the space inside your chest.
By Boyle’s law, this bigger space lowers the pressure inside the lungs. This is called the intrapulmonary pressure. It drops just below the pressure of the air outside. So air flows in until the two pressures are equal.
The lungs themselves have no muscle. They follow the chest wall. A thin film of fluid holds them to it. So does the intrapleural pressure, which always stays negative. When the chest gets bigger, the lungs get bigger with it.
Expiration: mostly letting go
Breathing out, or expiration, is the opposite. At rest it is easier, because it is usually passive. The diaphragm and external intercostals just relax. The stretched lungs and chest wall recoil, or spring back, like a rubber band you let go. The chest gets smaller. The pressure inside the lungs rises above the pressure outside, so air flows out.
A quiet breath out needs no muscle work at all. Sometimes you need to force air out, like when you blow out candles, cough, or exercise hard. Only then do the internal intercostals and abdominal muscles join in to squeeze the chest.
| Inspiration | Expiration (quiet) | |
|---|---|---|
| Effort | Active (muscles tighten) | Passive (muscles relax) |
| Main muscles | Diaphragm, external intercostals | None; the lungs spring back on their own |
| Thoracic volume | Goes up | Goes down |
| Intrapulmonary pressure | Falls below the air outside | Rises above the air outside |
| Air movement | In | Out |
Watch the diaphragm change the chest’s volume and pressure in the interactive below.
- Boyle’s law: making the chest bigger lowers lung pressure, so air flows in. Making it smaller raises pressure, so air flows out.
- Inspiration is active (diaphragm + external intercostals). Quiet expiration is passive (the lungs spring back).
- A negative intrapleural pressure keeps the lungs stuck to the chest wall. Break the seal, and the lung collapses (pneumothorax).
Section 4Gas exchange
Partial pressure: each gas pushes on its own
Air is a mix of gases. In a mix, each gas adds its own share to the total pressure. That share is its partial pressure. Each gas acts as if the others were not there.
Oxygen makes up about 21% of air. So at sea level, its partial pressure is about 160 mmHg in the open air. We write this as PO₂. Inside the alveoli, the oxygen is mixed with other gases, so its PO₂ falls to about 104 mmHg.
This matters because of how gases spread, or diffuse. A gas moves from where its partial pressure is high to where it is low. It keeps moving until the two sides even out. Every gas exchange in the body is this one rule, used over and over.
External respiration: loading O₂, dumping CO₂
External respiration is the swap that happens in the lungs. It takes place between the air in the alveoli and the blood. Blood coming back from the body is low in oxygen, with a PO₂ of about 40 mmHg. It is high in carbon dioxide, with a PCO₂ of about 45 mmHg. The air in the alveoli is the reverse. It is high in oxygen (about 104 mmHg) and low in carbon dioxide (about 40 mmHg).
So oxygen moves down its gradient into the blood. Carbon dioxide moves the other way, out into the alveoli, and you breathe it out. Blood leaves the lungs fully loaded with oxygen. It has given up only a small part of its carbon dioxide. That is just enough to bring PCO₂ down from about 45 to about 40 mmHg. Most of the blood’s carbon dioxide stays with it, stored in a large bicarbonate pool. You will meet this pool in Section 5. Each trip through the lungs trims the pool. It does not empty it.
Internal respiration: the reverse at the tissues
Internal respiration is the same physics run backward, out in the body’s tissues. Cells always burn oxygen and give off carbon dioxide. So in the tissues, PO₂ is low, about 40 mmHg. PCO₂ is high, about 45 mmHg.
The blood arriving in the tissue capillaries is the opposite. So oxygen moves out of the blood into the cells. Carbon dioxide moves into the blood to be carried back to the lungs. It is the same rule in the opposite direction. The cycle repeats with every heartbeat.
| Gas | Alveoli (air) | Deoxygenated blood | Tissues |
|---|---|---|---|
| PO₂ | ~104 mmHg | ~40 mmHg | ~40 mmHg |
| PCO₂ | ~40 mmHg | ~45 mmHg | ~45 mmHg |
| Net movement | O₂ in, CO₂ out (external) | — | O₂ out, CO₂ in (internal) |
Switch between the lungs and the tissues in the interactive below.
- Each gas moves from high to low partial pressure. It stops when the pressures are equal.
- External respiration (lungs): O₂ goes into the blood, and CO₂ goes out to be breathed out.
- Internal respiration (tissues): O₂ goes out to the cells, and CO₂ goes into the blood. It is the same rule in reverse.
Section 5Gas transport in the blood
Oxygen rides on hemoglobin
Oxygen barely dissolves in water. So blood plasma alone could never carry enough to keep you alive. Only about 1.5% of the oxygen in blood is dissolved. The other 98.5% is bound to hemoglobin. This is an iron-containing protein packed inside red blood cells.
Each hemoglobin molecule can hold up to four oxygen molecules on its iron sites. Hemoglobin loaded with oxygen is called oxyhemoglobin. This is the whole reason red blood cells exist. Hemoglobin lets blood carry about seventy times more oxygen than it could without it.
The oxygen–hemoglobin dissociation curve
Hemoglobin has a wonderful talent. It grabs oxygen tightly where oxygen is plentiful, in the lungs. It lets go of oxygen where oxygen is scarce, in the tissues. You can graph how full of oxygen hemoglobin is against the PO₂ around it. The result is an S-shaped line called the oxygen–hemoglobin dissociation curve.
Even better, hemoglobin responds to what the tissue needs. A hard-working tissue is warmer and more acidic. It also has more carbon dioxide. There, hemoglobin loosens its grip. It hands off more oxygen right where it is needed most. The shift caused by low pH and high CO₂ is the Bohr effect. Warmth shifts the curve the same way, but through a separate path. This is homeostasis, or keeping things in balance, on a tiny scale. The busiest cells automatically get the most oxygen.
Carbon dioxide travels three ways
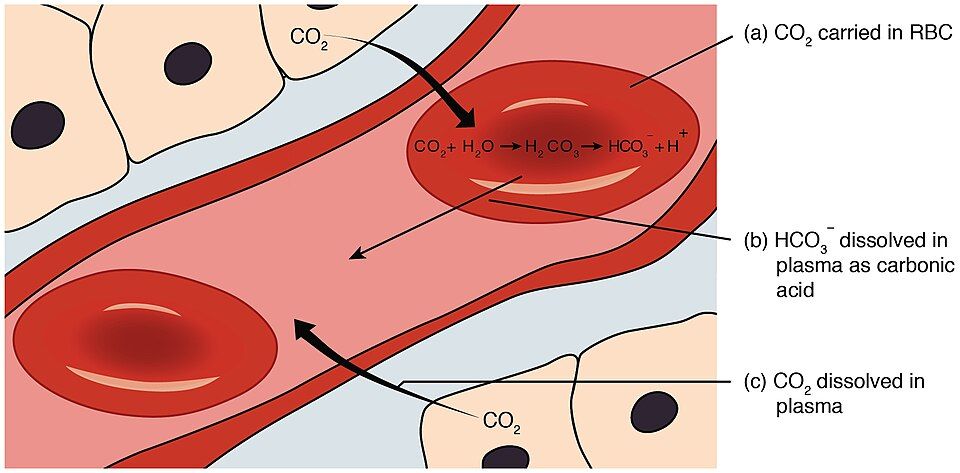
Carbon dioxide takes three different rides back to the lungs. A small share, about 7%, just dissolves in plasma. About 23% binds to hemoglobin as carbaminohemoglobin. It sits on a different spot than oxygen does.
Most of it, about 70%, is changed into bicarbonate inside red blood cells. The enzyme carbonic anhydrase joins CO₂ with water to make carbonic acid. The carbonic acid splits into a hydrogen ion and a bicarbonate ion (HCO₃⁻). The bicarbonate slips out into the plasma. At the lungs, the whole reaction runs in reverse. This frees CO₂ so you can breathe it out.
| Gas | Form in blood | Share |
|---|---|---|
| Oxygen | Bound to hemoglobin (oxyhemoglobin) | ~98.5% |
| Oxygen | Dissolved in plasma | ~1.5% |
| Carbon dioxide | As bicarbonate (HCO₃⁻) | ~70% |
| Carbon dioxide | Bound to hemoglobin (carbaminohemoglobin) | ~23% |
| Carbon dioxide | Dissolved in plasma | ~7% |
Switch between oxygen and carbon dioxide transport in the interactive below.
- Oxygen is carried mostly on hemoglobin (about 98.5%). Each molecule binds four O₂.
- In the Bohr effect, low pH plus high CO₂ make hemoglobin release more oxygen in hard-working tissues. The warmth of those tissues shifts the curve the same way, by a separate path.
- Carbon dioxide travels as bicarbonate (about 70%), on hemoglobin (about 23%), and dissolved (about 7%). This links breathing to blood pH.
Section 6Lung volumes & capacities
Four volumes
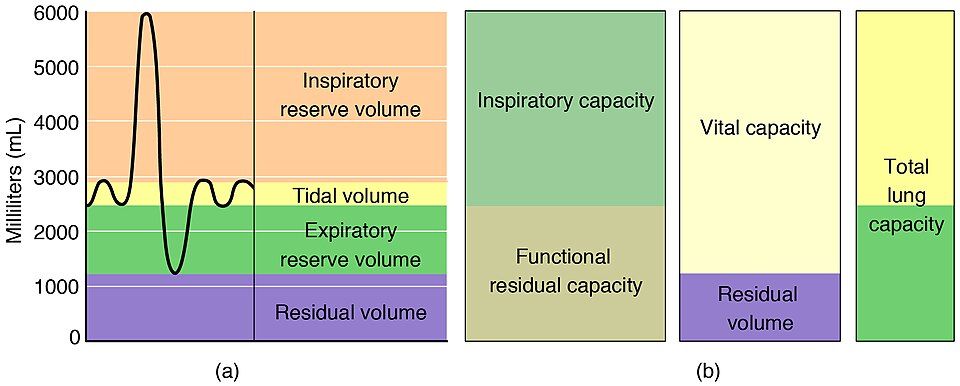
A spirometer is a device that records how much air you move as you breathe. Its tracing is split into four basic volumes. Tidal volume (TV) is the small amount you move in a normal, quiet breath. It is about 500 mL.
Inspiratory reserve volume (IRV, about 3000 mL) is the extra air you can pull in with your deepest breath. Expiratory reserve volume (ERV, about 1100 mL) is the extra you can force out after a normal breath out. Last, residual volume (RV, about 1200 mL) is the air that always stays behind. You can never fully empty your lungs. That leftover air keeps the alveoli from collapsing between breaths.
Four capacities (volumes added together)
A capacity is just two or more volumes added together. Each one answers a useful question. Vital capacity (VC) is the total you can move from your deepest breath in to your hardest breath out. It equals TV + IRV + ERV, about 4600 mL. It is the number doctors care about most.
Total lung capacity (TLC) adds the residual volume back in. It is everything the lungs can hold, about 5800 mL. Inspiratory capacity (IC = TV + IRV) is all you can breathe in from rest. Functional residual capacity (FRC = ERV + RV) is what is left after a normal breath out.
| Measure | Definition | Typical value |
|---|---|---|
| Tidal volume (TV) | Air in one normal, quiet breath | ~500 mL |
| Inspiratory reserve (IRV) | Extra air you can force in | ~3000 mL |
| Expiratory reserve (ERV) | Extra air you can force out | ~1100 mL |
| Residual volume (RV) | Air that cannot be breathed out | ~1200 mL |
| Vital capacity (VC) | TV + IRV + ERV | ~4600 mL |
| Total lung capacity (TLC) | VC + RV (everything) | ~5800 mL |
Dead space & what spirometry reveals
Not all the air you breathe in reaches the alveoli. About 150 mL stays in the conducting airways, where no gas exchange happens. This is the anatomical dead space. So of a 500 mL breath, only about 350 mL is fresh air that does real work.
Spirometry becomes truly powerful when it is timed. The FEV₁/FVC ratio tells how much of your vital capacity you can blow out in the first second. This ratio separates the two big families of lung disease. In obstructive disease, like asthma and COPD, the airways are narrow. Air comes out slowly, so the ratio drops. In restrictive disease, like fibrosis, the lungs are stiff and small. The volumes shrink, but the air that is there comes out quickly. So the ratio stays normal or high.
Trace each volume on a spirometer in the interactive below.
- There are four volumes: tidal, inspiratory reserve, expiratory reserve, and residual. Capacities are volumes added together (VC, TLC, IC, FRC).
- Residual volume always stays behind and keeps alveoli open. A simple spirometer cannot measure it.
- A low FEV₁/FVC ratio points to obstructive disease. Small volumes with a normal ratio point to restrictive disease.
The chapter in one breath
- The airway has a conducting zone that moves and conditions air. It also has a respiratory zone where gases are actually traded. Air travels nose → pharynx → larynx → trachea → bronchi → bronchioles → alveoli.
- Gases are traded across the paper-thin respiratory membrane of about 300 million alveoli. Surfactant from type II cells keeps the sacs from collapsing.
- Breathing follows Boyle’s law. Breathing in is active: the diaphragm and external intercostals make the chest bigger. A quiet breath out is passive: the lungs spring back.
- Gases move from high to low partial pressure. O₂ goes in and CO₂ goes out at the lungs (external respiration). The reverse happens at the tissues (internal respiration).
- Oxygen is carried mostly on hemoglobin. Carbon dioxide travels mostly as bicarbonate, which ties breathing to blood pH.
- The lung’s volumes and capacities measure how much air you move. A low FEV₁/FVC ratio points to obstructive disease. Small volumes point to restrictive disease.
ReferenceWords worth knowing
Here is a quick list of the terms in this chapter. Skim it now, or come back whenever a word trips you up.
- Alveolus
- A tiny, thin-walled air sac (plural: alveoli). Here oxygen and carbon dioxide are traded with the blood.
- Bicarbonate (HCO₃⁻)
- The ion that most carbon dioxide is turned into so it can travel in the blood. It also plays a key part in the body’s acid–base balance.
- Bohr effect
- Hemoglobin holds oxygen less tightly when H⁺ rises (lower pH) and carbon dioxide rises. So it releases more oxygen in active tissue. Warmth shifts the curve the same way, but by a separate path, not by the Bohr effect.
- Boyle’s law
- At a steady temperature, a gas’s pressure goes up as its volume goes down, and the reverse. It explains how the chest moves air.
- Bronchiole
- A small airway of the conducting zone with no cartilage. Smooth muscle sets how wide it is.
- Conducting zone
- The airways, from the nose through the bronchioles. They carry, warm, moisten, and filter air, but they do not trade gases.
- Dead space (anatomical)
- The roughly 150 mL of air breathed in that stays in the conducting airways. It never reaches the alveoli for exchange.
- Diaphragm
- The dome-shaped muscle under the lungs. When it tightens, it is the main force behind breathing in.
- Expiration
- Breathing out. It is passive at rest, as the lungs spring back, and active when forced.
- External respiration
- Gas exchange in the lungs, between the air in the alveoli and the blood. Oxygen goes in, and carbon dioxide comes out.
- Hemoglobin
- The iron-containing protein in red blood cells. It binds and carries up to four oxygen molecules.
- Inspiration
- Breathing in. It is an active process in which the diaphragm and external intercostals make the chest bigger.
- Internal respiration
- Gas exchange in the tissues, between blood and cells. Oxygen goes out to the cells, and carbon dioxide goes into the blood.
- Intrapleural pressure
- The pressure in the fluid-filled space between the lung and the chest wall. It stays negative, so the lung stays filled against the wall.
- Partial pressure
- The share of the total pressure that comes from one gas in a mix. Gases move from high to low partial pressure.
- Residual volume
- The air (about 1200 mL) left in the lungs after your hardest breath out. You cannot push it out by choice.
- Respiratory membrane
- The barrier, about 0.5 µm thick, that gases cross. It is made of the alveolar wall, the fused basement membranes, and the capillary wall.
- Spirometry
- A test that measures how much air a person breathes and how fast. It is used to diagnose lung disease.
- Surfactant
- A mix of fats and proteins made by type II alveolar cells. It lowers surface tension and keeps alveoli from collapsing.
- Tidal volume
- The amount of air (about 500 mL) moved in one normal, quiet breath.
- Vital capacity
- The most air a person can breathe out after their deepest breath in. It equals the tidal, inspiratory reserve, and expiratory reserve volumes added together.