Assessing the Musculoskeletal and Neurologic Systems
These two systems are assessed together because they fail together. A patient who cannot lift an arm may have a torn rotator cuff, a compressed nerve root, or an infarct in the contralateral motor cortex — and the exam that tells those apart is the same exam, performed in order, compared side to side, and repeated over time. This chapter teaches the actual hands: how to inspect a joint, grade a muscle from 0 to 5, take a Glasgow Coma Scale score that another nurse can reproduce, elicit a patellar reflex and grade it 0 to 4+, and run a neurovascular check on a casted limb in any skin tone. It also teaches the findings that end the exam and start a phone call — pain out of proportion under a cast, a new pronator drift, a widening pulse pressure with a falling heart rate — and exactly how to hand those off in SBAR.
By the end of this chapter you can
- Perform a screening musculoskeletal exam in the correct order — inspection, palpation, range of motion, strength — and state why the abdomen is the one region where the classic four-step sequence is reordered.
- Grade muscle strength on the 0–5 scale and deep tendon reflexes on the 0–4+ scale, and document both so another clinician gets the same number.
- Measure and describe joint range of motion in degrees for the cervical spine, shoulder, elbow, hip, knee and ankle, and distinguish active from passive ROM.
- Assess gait, balance and fall risk using the Timed Up and Go, the 4-stage balance test and orthostatic vital signs, using exact cutoffs.
- Determine level of consciousness with AVPU and the Glasgow Coma Scale, and screen cognition and delirium with Mini-Cog and the CAM.
- Test cranial nerves I–XII, motor and cerebellar function, the sensory system and reflexes, and interpret findings as upper versus lower motor neuron.
- Describe expected variations across the lifespan — infant primitive reflexes, fontanels, pregnancy, the older adult — and assess pallor, cyanosis and erythema accurately in dark skin tones.
- Recognize the red flags that require escalation now — compartment syndrome, cauda equina syndrome, autonomic dysreflexia, stroke by BE-FAST, rising intracranial pressure — and escalate using SBAR.
- Apply delegation rules: what a UAP may do with a mobility-impaired or neurologically changing patient and what stays with the RN.
Section 1The Musculoskeletal Exam — Structure, Sequence and Strength
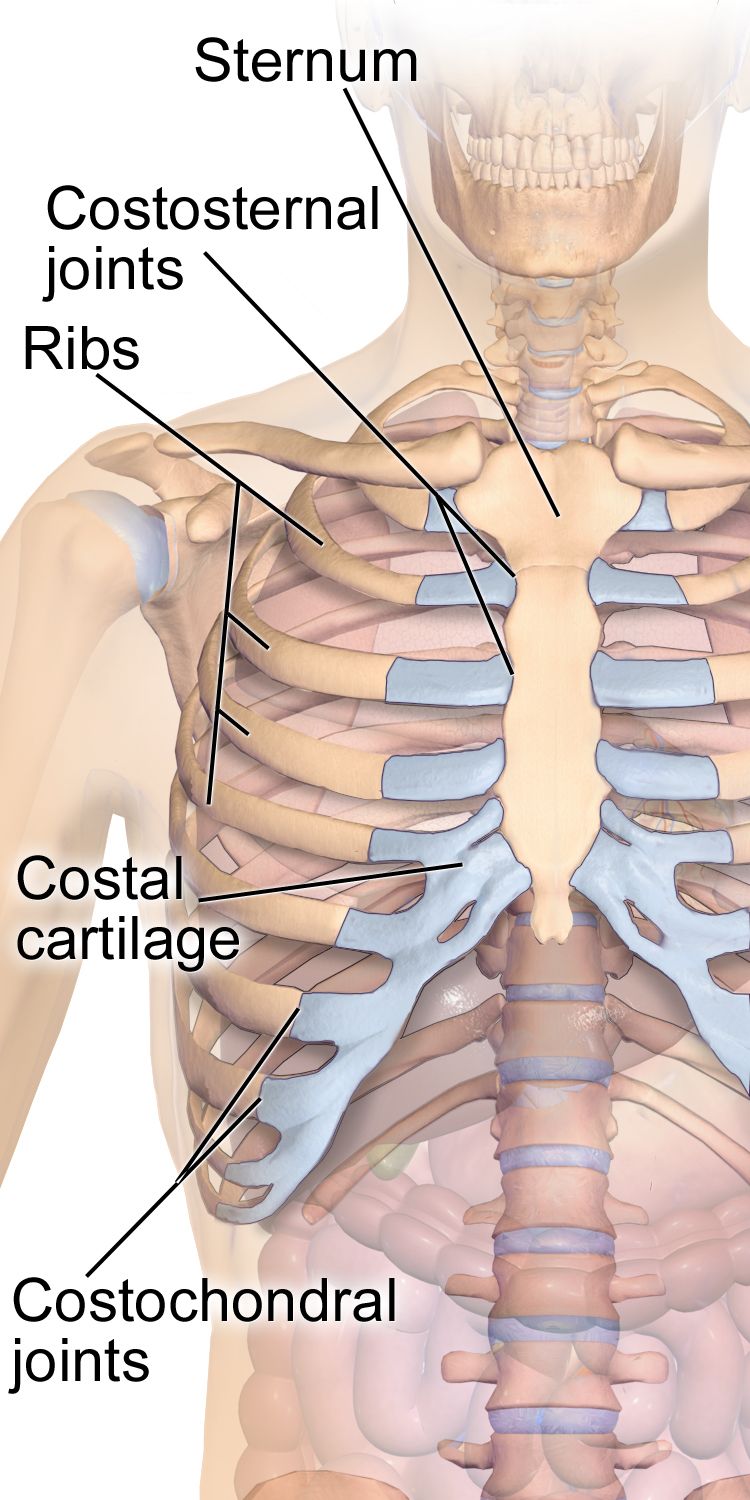
What you are actually assessing
The musculoskeletal system is 206 bones, roughly 640 skeletal muscles, and the joints, tendons, ligaments, bursae and cartilage that connect them. At the bedside you are almost never assessing all of it. You are doing one of two exams. The screening exam is what you perform on admission and at the start of a shift on a stable patient: observe posture and gait, watch the patient move in and out of bed and reach overhead, look at the hands, and check symmetry. It takes about ninety seconds and it is enough to catch asymmetry, guarding, deformity and functional loss. The focused exam is what you perform when the screening exam, the history or the diagnosis points somewhere: a fall with hip pain, a new cast, a shoulder that will not abduct, a complaint of numb fingers at night.
Two habits make the musculoskeletal exam reliable. First, always compare side to side. The patient’s own opposite limb is the only control group you have, and it is a very good one. A knee that measures three centimeters larger in circumference than its partner is an objective finding; “knee looks swollen” is an opinion. Second, examine the joint above and the joint below the painful one. Hip pathology refers pain to the knee, cervical pathology refers pain to the shoulder and hand, and a patient who points at one place is not always pointing at the problem.
Position matters more than students expect. Expose the joint fully — you cannot assess what is under a gown or a blanket — while draping everything you are not examining. Ask about pain before you touch, and examine the non-painful side first so the patient learns what your hands feel like on tissue that does not hurt. Never force a joint through a range the patient cannot reach voluntarily; passive range of motion is performed slowly, to the point of resistance or the report of pain, and then you stop.
The sequence — and the one region that breaks it
The classic physical assessment sequence is inspection, palpation, percussion, auscultation, and it is used in that order in every body region except the abdomen. In the abdomen the order becomes inspection, auscultation, percussion, palpation, because percussing and palpating first stimulates the bowel and alters the bowel sounds you were about to listen for — you would be auscultating a gut you already provoked. Nowhere else does that problem exist, so nowhere else is the order changed.
Applied to a joint, the four steps look like this. Inspection: with the patient upright and the joint exposed, compare size, contour, alignment and symmetry with the opposite side; look for swelling, redness, muscle wasting, deformity and the way the patient holds the part at rest. Palpation: using the pads of the fingers and the back of your hand for temperature, palpate the joint line, the bony landmarks, the tendon insertions and the surrounding muscle for warmth, effusion, tenderness, nodules and crepitus — a palpable or audible grating with movement. Percussion: in the musculoskeletal and neurologic exam, percussion is done with the reflex hammer over tendons (Section 4) and, in specific situations, over the spinous processes to reproduce focal bony tenderness. Auscultation: limited but real — auscultate the carotids for a bruit before any vigorous neck range of motion in an older adult, and listen over a joint replacement or a suspected arteriovenous malformation if there is a clinical reason.
Then two steps that belong specifically to the musculoskeletal exam are added after palpation: range of motion (active first, then passive if active is limited) and muscle strength against resistance. Active before passive is not arbitrary. Active ROM tells you what the patient can do — a functional answer. If active ROM is full, you do not need passive ROM. If active ROM is limited but passive ROM is full, the joint moves and the problem is muscle, nerve, pain or effort. If both are limited, the problem is in the joint itself: contracture, effusion, mechanical block, ankylosis.
Grading with numbers, not adjectives
Muscle strength is graded 0 to 5 against gravity and resistance, and every nurse in the building uses the same scale. Test the muscle group in isolation, stabilize the joint above it, and apply resistance through the mid-range while the patient holds. Grade each side separately: “5/5 right, 4/5 left” is information; “strength good” is not. Range of motion is recorded in degrees, from a defined zero (anatomic position) to the end of movement. You do not need a goniometer for a screening exam, but you do need to know what full looks like so you can say “knee flexion approximately 90 degrees, limited by pain” instead of “knee doesn’t bend all the way.”
| Grade | What the patient does | Common shorthand |
|---|---|---|
| 5 | Full ROM against gravity and full resistance | Normal (5/5) |
| 4 | Full ROM against gravity and some resistance | Good (4/5) |
| 3 | Full ROM against gravity only — no resistance tolerated | Fair (3/5) |
| 2 | Full ROM only with gravity eliminated (limb supported sideways) | Poor (2/5) |
| 1 | Palpable or visible flicker of contraction, no joint movement | Trace (1/5) |
| 0 | No detectable contraction | Zero (0/5) — paralysis |
| Joint and motion | Expected adult range | What limitation may mean |
|---|---|---|
| Cervical flexion / extension | 45° / 55° | Muscle spasm, arthritis; rigidity plus fever suggests meningeal irritation |
| Cervical rotation / lateral bending | 70° each side / 40° each side | Degenerative disc disease, torticollis |
| Shoulder flexion and abduction | 180° | Painful arc 60–120° suggests rotator cuff impingement |
| Elbow flexion / extension | 150–160° / to 0° | Effusion, contracture, heterotopic ossification |
| Wrist flexion / extension | 80–90° / 70° | Carpal tunnel syndrome, rheumatoid synovitis |
| Hip flexion (knee flexed / knee straight) | 120° / 90° | Osteoarthritis, effusion, flexion contracture |
| Knee flexion | 130–150° | Effusion, meniscal tear, post-arthroplasty stiffness |
| Ankle dorsiflexion / plantar flexion | 20° / 45° | Achilles pathology, cast immobilization, foot drop |
| Lumbar flexion / extension | 75–90° / 30° | Disc disease, spasm, ankylosing spondylitis |
How to chart it
Musculoskeletal documentation fails in a predictable way: it is written as a conclusion instead of an observation. “Musculoskeletal within normal limits” is unfalsifiable, unhelpful in court, and useless to the nurse who follows you and needs to know whether the left grip changed. Write what you did, what you measured, and on which side.
| Vague entry | Precise entry a nurse can act on |
|---|---|
| “MSK WNL. Moves all extremities.” | “Moves all four extremities to command. Strength 5/5 bilateral grips, 5/5 bilateral plantar flexion and dorsiflexion. No joint swelling, deformity or tenderness. Gait steady with single-point cane, no assist required.” |
| “Right knee swollen and sore.” | “Right knee warm to touch compared to left, circumference 42 cm right vs 38.5 cm left at mid-patella. Positive bulge sign. Active flexion 85° limited by pain rated 6/10; passive flexion 95°. Ambulates 10 feet with walker, antalgic gait favoring right. Left knee unremarkable.” |
| “Weak on the left.” | “Left grip 3/5, right grip 5/5. Left elbow flexion 4/5, right 5/5. Left leg 4/5 hip flexion, 5/5 elsewhere. New compared to 0800 assessment (all 5/5). Provider notified 1412.” |
Inspect, palpate, percuss, auscultate in every region except the abdomen — and in the musculoskeletal exam add active range of motion, then passive, then graded strength, always comparing left to right.
Section 2Region by Region — Spine, Limbs, Gait and the Neurovascular Check
Spine and posture
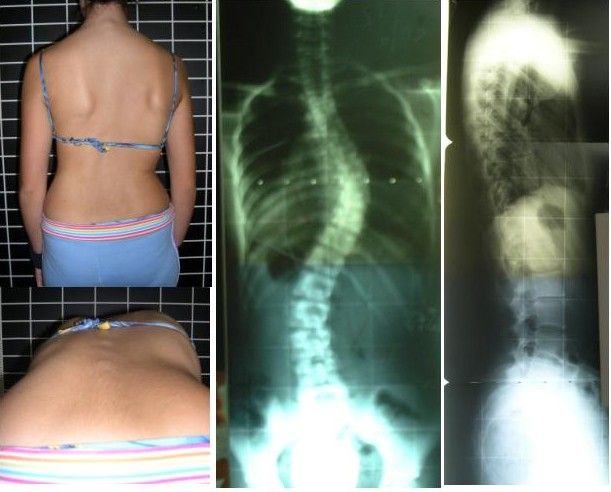
Inspect the spine with the patient standing and undressed to the underwear, from behind and from the side. From behind, the spinous processes should form a straight vertical line; the shoulders, scapulae and iliac crests should be level; the gluteal fold should be symmetric. From the side, expect the normal curves: cervical concave, thoracic convex, lumbar concave. Kyphosis is an exaggerated thoracic convexity, lordosis an exaggerated lumbar concavity, scoliosis a lateral curvature with vertebral rotation. Palpate down the spinous processes and the paravertebral muscles for tenderness and spasm.
Screen for scoliosis with the Adams forward bend test: the patient stands with feet together and bends forward at the waist with knees straight and arms hanging. You look tangentially across the back for a unilateral rib hump or lumbar prominence, which reveals the vertebral rotation that a standing exam hides. Adolescent idiopathic scoliosis is screened around ages 10 and 12 in girls and 13 or 14 in boys, because curves progress during the growth spurt. Test lumbar range of motion — flexion 75–90°, extension 30°, lateral bending 35° each way, rotation 30° each way — stabilizing the pelvis so the motion comes from the spine.
For radicular low back pain, the straight leg raise is the test to know. The patient lies supine; you raise the extended leg by the heel with the knee straight. Reproduction of the patient’s shooting pain below the knee between 30 and 70 degrees of elevation is a positive test suggesting lumbar nerve root irritation (usually L5 or S1). Hamstring tightness or posterior thigh pulling is not a positive test. Pain reproduced in the affected leg when you raise the opposite leg (crossed straight leg raise) is less sensitive but much more specific for disc herniation.
Upper extremity
At the shoulder, inspect for the squared-off contour of a dislocation and for deltoid wasting. Palpate the sternoclavicular and acromioclavicular joints, the bicipital groove and the subacromial space. Screen ROM with three commands that cover everything: “raise both arms straight overhead” (flexion and abduction to 180°), “touch the back of your neck” (external rotation and abduction), “touch the middle of your back” (internal rotation and adduction). Pain only between 60 and 120 degrees of abduction — a painful arc — suggests subacromial impingement. In the drop arm test, you passively abduct the arm to 90 degrees and ask the patient to lower it slowly; if the arm drops abruptly, suspect a rotator cuff tear.
At the elbow, palpate the olecranon and the epicondyles; tenderness over the lateral epicondyle with resisted wrist extension suggests lateral epicondylitis. At the wrist and hand, inspect for the ulnar deviation and swan-neck or boutonniere deformities of rheumatoid arthritis, the hard Heberden nodes at the distal interphalangeal joints and Bouchard nodes at the proximal interphalangeal joints of osteoarthritis, and thenar wasting. For suspected carpal tunnel syndrome, Phalen test holds the wrists in full flexion back to back for 60 seconds and is positive if numbness or tingling develops in the thumb, index, middle and radial half of the ring finger; Tinel sign taps lightly over the median nerve at the volar wrist and is positive if the same tingling shoots into those digits.
Lower extremity and gait
At the hip, inspect stance and leg length, palpate the greater trochanter for bursal tenderness, and test flexion, internal rotation (40°) and external rotation (45°) — internal rotation is usually lost first in hip osteoarthritis. The Trendelenburg sign is positive when the patient stands on one leg and the opposite hip drops, indicating weakness of the gluteus medius on the weight-bearing side. At the knee, inspect for effusion and quadriceps atrophy, palpate the joint line, and use the bulge sign for a small effusion: milk fluid upward from the medial side, then stroke down the lateral side and watch for a fluid wave to appear medially. Larger effusions are detected by ballottement of the patella. Ligament and meniscal testing — anterior drawer and Lachman for the anterior cruciate ligament, McMurray for the meniscus — is generally performed by the provider, but you should recognize the names in the chart.
Then watch the patient walk, because gait integrates everything. Observe a full walking cycle from the front, side and back for stride length, arm swing, foot clearance, base width and symmetry. Named abnormal gaits carry diagnoses: antalgic (short time in stance on the painful side), steppage (high knee lift to clear a dropped foot — peroneal nerve or L5), shuffling with reduced arm swing (parkinsonian), wide-based and unsteady (cerebellar ataxia), scissoring (spastic diplegia), and the stiff circumducted swing of a hemiparetic gait after stroke.
Fall risk deserves exact numbers. In the Timed Up and Go (TUG), the patient rises from a standard armchair, walks 10 feet (3 meters), turns, walks back and sits down, wearing usual footwear and using their usual assistive device. 12 seconds or more indicates increased fall risk (CDC STEADI). The 4-Stage Balance Test asks for feet together, semi-tandem, full tandem and single-leg stance, 10 seconds each; inability to hold full tandem for 10 seconds is a fall-risk finding. Orthostatic vital signs are positive when, within 3 minutes of standing, systolic BP falls 20 mmHg or more, diastolic BP falls 10 mmHg or more, or heart rate rises 20 beats/min or more. Measure supine after 5 minutes rest, then sitting, then standing — and stay with the patient the whole time.
The neurovascular check — and skin tone
Any patient with a fracture, cast, splint, traction, surgical extremity, circumferential dressing or vascular procedure gets scheduled neurovascular checks distal to the injury, compared to the opposite limb. The elements are colour, temperature, capillary refill, pulses, sensation, movement, pain and edema — often charted as CMS (circulation, motion, sensation). Expected: warm, colour matching the other limb, capillary refill under 2 seconds (longer than 2 seconds is abnormal, and 3 seconds or more is clearly delayed), palpable distal pulse equal to the other side, intact light touch and two-point sensation, active wiggle of fingers or toes, and pain that is controlled by the ordered analgesia. Frequency is typically every hour for the first 24 hours after casting or surgery, then every 4 hours, or per facility protocol — and immediately with any patient complaint.
Colour findings must be assessed correctly in every skin tone, because “pink” is a description of light skin, not a physiologic standard. In darker skin, pallor appears as ashen or grey rather than white; cyanosis appears as grey, dusky or blue-black. The reliable sites in every patient are the oral mucosa and tongue, the conjunctivae, the palms and soles, and the nail beds. Jaundice is best seen in the sclera (against the hard palate and palms if the sclera is equivocal), and in darker skin the sclera may have normal yellowish fat deposits near the periphery — look near the cornea. Erythema and early inflammation may be invisible in darker skin, so assess by palpation: compare the area to surrounding skin for warmth, induration, edema, tautness and tenderness, and use natural or full-spectrum light rather than fluorescent. Ask the patient what their normal skin colour looks like.
| Neurovascular element | Expected finding | Abnormal finding and what it suggests |
|---|---|---|
| Colour | Matches the contralateral limb; oral mucosa, conjunctivae, palms/soles and nail beds unchanged from this patient’s own baseline — never judged against “pink” | Newly pale, ashen or grey against the other limb → arterial compromise; dusky, grey or blue-black at mucosa, conjunctivae or nail beds → venous congestion or hypoxia |
| Temperature | Warm, equal to opposite limb (back of hand) | Cool distal to injury → arterial insufficiency or tight cast |
| Capillary refill | Under 2 seconds | Longer than 2 seconds, and certainly 3 or more → poor perfusion (also cold environment, shock) |
| Pulses | Palpable, 2+ and equal bilaterally | Diminished or absent → late, ominous sign of compartment syndrome or arterial injury |
| Sensation | Intact light touch, no numbness or tingling | Paresthesia, numbness → nerve compression — an early compartment sign |
| Movement | Wiggles digits actively and fully | Weak or absent movement → late nerve or muscle ischemia |
| Pain | Relieved by ordered analgesia and elevation | Pain out of proportion, unrelieved, worse with passive stretch of the digits → compartment syndrome until proven otherwise |
Regional musculoskeletal assessment is comparison plus function — measure the joint in degrees, watch the patient walk, and on any immobilized limb run a scheduled neurovascular check whose colour findings you assess at the mucosa, conjunctivae, palms and nail beds rather than by expecting “pink.”
Section 3The Neurologic Exam Begins — Consciousness, Cognition and Cranial Nerves
Level of consciousness first, always
Level of consciousness is the single most sensitive indicator of neurologic change, and it is assessed before anything else, because the rest of the exam depends on it. Consciousness has two parts: arousal (are they awake?) and awareness (do they know what is going on?). Start with the least invasive stimulus and escalate only as needed — voice at normal volume, then loud voice, then touch, then a central painful stimulus such as a trapezius squeeze or supraorbital pressure. Sternal rub is also a central stimulus, but it is no longer recommended as a routine tool because repeated rubbing bruises the skin. What you must not do is substitute a peripheral stimulus — nail-bed or nail-fold pressure — for a central one when you are scoring the motor response, because a limb can withdraw on a spinal reflex arc with no brain involvement at all.
AVPU is the fast screen: Alert, responds to Voice, responds to Pain, Unresponsive. The Glasgow Coma Scale is the standardized score, from 3 (worst possible) to 15 (fully intact), built from three components. Score the best response in each category, score each side’s best motor response but chart the best overall, and record the components, not just the total: a GCS of 9 made of E2 V2 M5 is a very different patient from E4 V1 M4, and “GCS 9” alone hides that. A GCS of 8 or less generally indicates an inability to protect the airway and prompts consideration of intubation. A drop of 2 or more points in the total, or any drop in the motor score, is an urgent change.
| Eye opening (E) | Verbal response (V) | Best motor response (M) |
|---|---|---|
| 4 — Spontaneous | 5 — Oriented | 6 — Obeys commands |
| 3 — To sound / speech | 4 — Confused conversation | 5 — Localizes to pressure |
| 2 — To pressure | 3 — Inappropriate words | 4 — Normal flexion / withdraws |
| 1 — None | 2 — Incomprehensible sounds | 3 — Abnormal flexion (decorticate) |
| NT — Not testable (swelling) | 1 — None · NT if intubated (chart “T”) | 2 — Extension (decerebrate) · 1 — None |
In the infant and preverbal child, the pediatric GCS substitutes developmentally appropriate responses: verbal 5 is coos and babbles, 4 irritable cries, 3 cries to pain, 2 moans to pain, 1 none; motor 6 becomes spontaneous purposeful movement and 5 becomes withdraws to touch. In critical care, sedation depth is scored separately with the RASS, from +4 (combative) through 0 (alert and calm) to −5 (unarousable) — a sedated patient’s low GCS may be pharmacologic, and you must know which.
Orientation, cognition and the delirium screen
“Alert and oriented ×4” means oriented to person, place, time and situation. Ask, do not assume: name, where we are right now, the month and year, and why they came to the hospital. Orientation is lost in a rough order — time first, then place, then situation, then person — so a patient who does not know the year but knows everything else is early, and a patient who does not know their own name is either profoundly impaired or not organically confused at all.
Screen cognition with the Mini-Cog: three unrelated words to remember, a clock-drawing task (“draw a clock face with all the numbers, then set the hands to ten past eleven”), then recall of the three words. Score 0–5 (one point per recalled word, two points for a normal clock); a total of 2 or less is a positive screen for cognitive impairment, while 3, 4 or 5 is a negative screen. The MMSE is scored out of 30 with less than 24 suggesting impairment; the MoCA is scored out of 30 with 26 or above considered normal and is more sensitive to mild impairment. None of these diagnoses dementia — they trigger further evaluation.
Delirium is the finding students miss most, because a quietly hypoactive delirious patient looks like a cooperative one. Use the Confusion Assessment Method (CAM): delirium is present when there is (1) acute onset or fluctuating course AND (2) inattention, PLUS either (3) disorganized thinking OR (4) altered level of consciousness. Test inattention concretely — months of the year backward from December, or digit span. Delirium is acute, fluctuating and usually reversible; dementia is chronic, progressive and stable hour to hour; depression can mimic both with poor effort and “I don’t know” answers. Also separate aphasia (a language disorder — expressive/Broca with effortful, halting, telegraphic speech and preserved comprehension; receptive/Wernicke with fluent but nonsensical speech and impaired comprehension) from dysarthria (a motor articulation problem with intact language). An aphasic patient may be fully oriented and unable to show you.
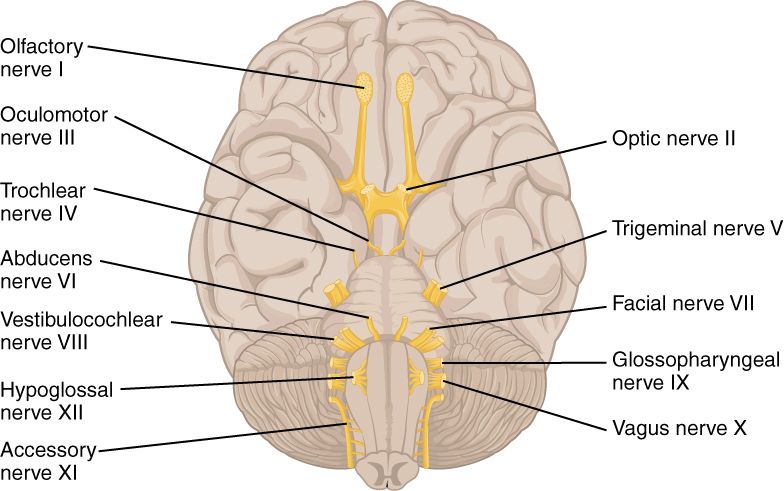
Cranial nerves I–XII
Test them in numerical order so you never skip one. On a routine medical-surgical patient the screening version takes two minutes: pupils, extraocular movements, facial symmetry, hearing to conversation, swallow, shoulder shrug and tongue protrusion. A focused exam — new neurologic complaint, suspected stroke, head injury, cranial surgery — tests all twelve.
| Nerve | How you test it | Expected | Abnormal suggests |
|---|---|---|---|
| I Olfactory | Eyes closed, one nostril at a time, familiar non-irritating scent (coffee) | Identifies scent both sides | Anosmia — frontal lesion, basilar skull fracture, viral |
| II Optic | Visual acuity (Snellen), gross visual fields by confrontation | 20/20 corrected; full fields | Hemianopsia — stroke, tumor, optic pathway lesion |
| III, IV, VI Oculomotor, Trochlear, Abducens | Six cardinal directions of gaze; pupil size, shape, direct and consensual reaction, accommodation | Conjugate gaze; pupils 2–5 mm, round, equal, briskly reactive (PERRLA) | Unilateral fixed dilated pupil → CN III compression / herniation — emergency; pinpoint <2 mm → opioids or pontine lesion |
| V Trigeminal | Light touch to forehead, cheek, jaw bilaterally; clench teeth and palpate masseters; corneal reflex (wisp) if indicated | Symmetric sensation; strong equal masseters | Unilateral numbness, weak jaw — brainstem lesion, trigeminal neuralgia |
| VII Facial | Raise eyebrows, close eyes tightly, smile, show teeth, puff cheeks; taste anterior two-thirds of tongue | Symmetric movement | Forehead spared → central lesion (stroke); whole side including forehead → peripheral (Bell palsy) |
| VIII Vestibulocochlear | Whispered word at 1–2 feet; Weber and Rinne with a 512 Hz tuning fork; balance | Hears whisper both sides; Weber midline; air conduction longer than bone (AC > BC) | Conductive vs sensorineural loss; vertigo, nystagmus |
| IX, X Glossopharyngeal, Vagus | Say “ahh” and watch the uvula and palate; voice quality; gag reflex if indicated | Palate rises symmetrically, uvula midline, clear voice | Uvula deviates away from the weak side; hoarseness, wet voice → aspiration risk |
| XI Spinal accessory | Shrug shoulders against resistance; turn head against resistance | Strong, symmetric 5/5 | Weak trapezius/sternocleidomastoid — nerve injury, neck surgery |
| XII Hypoglossal | Protrude tongue; move side to side; say “light, tight, dynamite” | Tongue midline, clear articulation | Tongue deviates toward the weak side; slurred lingual sounds |
Lifespan variation in the neurologic exam
Normal is age-dependent, and calling a normal infant finding pathologic (or missing a retained reflex) is a real error. In the newborn, the posterior fontanel closes by 2–3 months and the anterior fontanel by 12–18 months; a bulging tense fontanel in a quiet upright infant suggests raised intracranial pressure, a sunken one suggests dehydration. Primitive reflexes appear and then must disappear: Moro (startle) fades by 3–6 months, palmar grasp by 3–4 months, rooting by 3–4 months, tonic neck by 4–6 months, plantar grasp by 8–12 months. An upgoing great toe on plantar stimulation (Babinski response) is normal until roughly 12–24 months and abnormal after that. Persistence of a primitive reflex past its window, or asymmetry of any of them, is a referral.
In toddlers and children, bowed legs (genu varum) are expected until about age 2–3 and knock-knees (genu valgum) between about 2 and 7 years, peaking around 3–4 — both usually self-correct. In infancy screen the hips for developmental dysplasia with the Ortolani and Barlow maneuvers up to about 3 months, and after that with asymmetric thigh folds, limited hip abduction and a positive Galeazzi sign (unequal knee heights with hips and knees flexed).
In pregnancy, relaxin and progesterone loosen the pelvic ligaments and the center of gravity shifts forward, producing lumbar lordosis, low back pain, a wide-based waddling gait and increased fall risk; carpal tunnel symptoms are common from fluid retention. In the older adult, expect a loss of about 1 cm of height per decade after age 40, mild kyphosis, reduced muscle mass (sarcopenia), slower reaction time, smaller and more sluggishly reactive pupils, diminished vibratory sense in the feet, and ankle jerks that may be symmetrically diminished or absent — that last finding is common and, when bilateral and isolated, not necessarily pathologic. What is never normal at any age: new asymmetry, new confusion, and a new focal deficit.
Assess level of consciousness before anything else, chart the GCS in components rather than a bare total, screen every acute mental status change as delirium until proven otherwise, and interpret every neurologic finding against the patient’s age.
Section 4Motor, Cerebellar, Sensory and Reflex Testing
The motor exam — bulk, tone, strength and drift
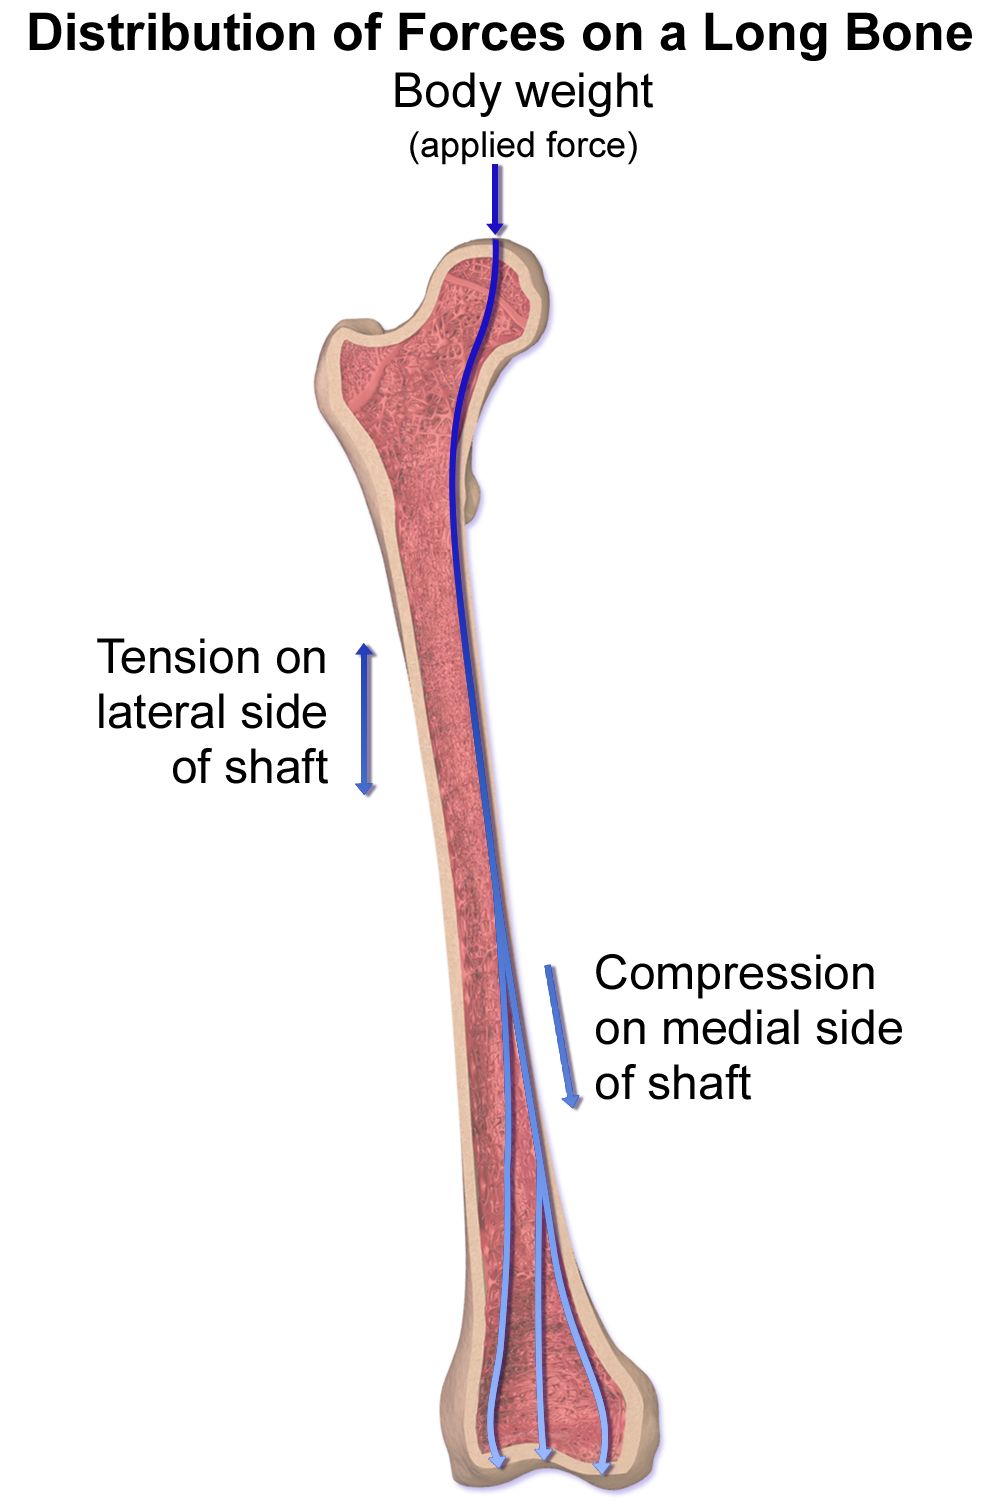
Assess motor function in four steps. Bulk: inspect and compare muscle mass bilaterally; measure limb circumference at a fixed landmark if you suspect atrophy. Tone: with the patient relaxed, move each limb passively through range and feel the resistance. Expect mild, even resistance. Flaccidity is absent tone (a lower motor neuron finding); spasticity is velocity-dependent resistance that gives way suddenly (clasp-knife, an upper motor neuron finding); rigidity is resistance throughout the range, either lead-pipe or ratcheting cogwheel rigidity of parkinsonism. Strength: graded 0–5 as in Section 1, tested group by group and compared side to side. Involuntary movement: note tremor at rest (parkinsonian) versus tremor that worsens as the hand approaches a target (intention tremor, cerebellar), plus fasciculations, tics and myoclonus.
The most useful single motor screen on a hospital unit is pronator drift. The patient extends both arms forward, palms up, eyes closed, for 20–30 seconds. Downward drift with pronation of one forearm indicates a corticospinal tract lesion on the opposite side of the brain, and it appears when formal strength testing still measures 5/5. It costs thirty seconds and it catches early strokes. Test the legs in the same spirit: heel slides, or holding both legs elevated off the bed and watching for one to sink.
| Feature | Upper motor neuron lesion (brain, spinal cord) | Lower motor neuron lesion (anterior horn, root, peripheral nerve) |
|---|---|---|
| Tone | Increased — spasticity | Decreased — flaccidity |
| Reflexes | Hyperactive (3+ to 4+), clonus possible | Diminished or absent (0 to 1+) |
| Plantar response | Upgoing great toe — positive Babinski | Downgoing (flexor) or absent |
| Muscle bulk | Normal early; disuse atrophy late | Marked atrophy |
| Fasciculations | Absent | Present |
| Pattern of weakness | Whole limb or one side of the body | Follows a specific nerve or root distribution |
Cerebellar function, balance and coordination
The cerebellum coordinates; it does not generate power. So cerebellar testing asks for accuracy and rhythm, not force. Rapid alternating movements: the patient pats the thigh alternating palm and back of hand as fast as possible, or taps thumb to each finger in sequence. Slow, clumsy, irregular performance is dysdiadochokinesia. Finger-to-nose: the patient alternates touching their nose and your fingertip while you move it; overshooting the target is dysmetria. Heel-to-shin: supine, the patient runs one heel down the opposite shin from knee to ankle; wavering off the line is a cerebellar finding. Gait and tandem walk: ask for heel-to-toe walking along a straight line.
The Romberg test is frequently misdescribed. The patient stands with feet together and arms at the sides, eyes open for about 20 seconds, then eyes closed for about 20 seconds. It is positive when the patient is steady with eyes open but sways markedly or loses balance with eyes closed — and that pattern means proprioceptive (dorsal column) or vestibular dysfunction, not cerebellar disease. A patient who is unsteady even with the eyes open has a cerebellar problem. Stand close enough to catch the patient every single time; a fall during a Romberg test is a preventable injury and it belongs to you.
The sensory exam
Sensory testing requires an alert, cooperative patient with eyes closed, and it is done by comparing symmetric areas side to side and distal to proximal. Do not tell the patient where you are touching. Screen a routine patient at the shoulders, forearms, hands, thighs, lower legs and feet; test in detail only where symptoms, a dermatome or a known lesion sends you. Ask “does this feel the same on both sides?” rather than “can you feel this?”
Primary sensations: light touch with a cotton wisp; pain with the sharp and dull ends of a broken tongue blade or a disposable neuro pin (never a reused sharp); temperature only if pain sensation is abnormal; vibration with a 128 Hz tuning fork placed on a bony prominence such as the great toe interphalangeal joint or the medial malleolus — ask when the buzzing stops; proprioception by moving the patient’s great toe or finger up or down while holding it by the sides and asking which way it moved. Vibration and proprioception travel in the dorsal columns and are the first to go in diabetic peripheral neuropathy and vitamin B12 deficiency, which is why an annual monofilament and vibration check is standard diabetic foot care.
Cortical (discriminative) sensations are tested only when primary sensation is intact, because they require an intact parietal cortex to interpret normal input: stereognosis (identify a coin or key placed in the hand), graphesthesia (identify a number traced on the palm), two-point discrimination, and extinction (touch both sides simultaneously; failing to report one side despite intact single-side sensation suggests a contralateral parietal lesion and often accompanies neglect after a right-hemisphere stroke). Translate the patient’s numb area into a root using the dermatome map: C6 thumb, C7 middle finger, C8 little finger, T4 nipple line, T10 umbilicus, L4 medial malleolus, L5 dorsum of the foot and great toe, S1 lateral foot and heel, S2–S4 perianal saddle.
Reflexes — the percussion half of the neuro exam
Deep tendon reflexes are elicited by striking a tendon with the flat or pointed end of a reflex hammer, using a loose wrist and letting the hammer fall by its own weight. The limb must be relaxed and the tendon slightly stretched; position, not force, is what makes a reflex appear. If a reflex seems absent, use reinforcement before you chart a zero: have the patient clench the teeth or interlock the fingers and pull apart (the Jendrassik maneuver) at the instant you strike. Grade each reflex, compare bilaterally, and remember that asymmetry is more meaningful than the absolute grade.
| Grade | Response | Interpretation |
|---|---|---|
| 0 | No response | Absent — lower motor neuron lesion, peripheral neuropathy, spinal shock |
| 1+ | Diminished, present only with reinforcement | Hypoactive — may be normal in some older adults if symmetric |
| 2+ | Brisk, expected response | Normal |
| 3+ | Brisker than average, no clonus | May be normal in an anxious patient; upper motor neuron lesion if asymmetric |
| 4+ | Hyperactive with sustained clonus | Always abnormal — upper motor neuron lesion; in pregnancy, think preeclampsia |
| Reflex | Where you strike | Nerve roots | Expected response |
|---|---|---|---|
| Biceps | Your thumb over the biceps tendon in the antecubital fossa | C5–C6 | Elbow flexion |
| Brachioradialis | Radius, about 1–2 inches above the wrist | C5–C6 | Forearm supination and elbow flexion |
| Triceps | Triceps tendon just above the olecranon, arm hanging | C6–C7 (mainly C7) | Elbow extension |
| Patellar | Patellar tendon below the patella, knee flexed and dangling | L2–L4 (mainly L4) | Knee extension |
| Achilles | Achilles tendon with the foot slightly dorsiflexed | S1–S2 (mainly S1) | Plantar flexion |
| Plantar (superficial) | Stroke the lateral sole from heel to ball, then across the metatarsal heads | L5–S1 | Toe flexion in adults; upgoing toe with fanning is abnormal after about 2 years of age |
Test for clonus whenever reflexes are 3+ or 4+: support the knee in slight flexion and briskly dorsiflex the ankle, holding the stretch. Rhythmic beats of plantar flexion follow; a few unsustained beats can be normal, but sustained clonus is an upper motor neuron finding and, in a pregnant patient with hypertension and headache, a warning of impending eclampsia. Chart reflexes concretely: “DTRs 2+ and symmetric at biceps, triceps, patellar and Achilles. Plantar reflexes downgoing bilaterally. No clonus.”
Motor, cerebellar, sensory and reflex testing sort a deficit into upper versus lower motor neuron, and the pattern — spastic with 4+ reflexes and an upgoing toe, versus flaccid with absent reflexes and fasciculations — tells you where the lesion lives.
Section 5Red Flags, Serial Checks and Escalation
Musculoskeletal emergencies
Acute compartment syndrome is the one every orthopedic patient is at risk for and the one students must be able to recognize without being told. Pressure rises inside a closed fascial compartment — from fracture bleeding, crush injury, a tight cast or a circumferential dressing — until it exceeds capillary perfusion pressure and the muscle and nerve inside begin to die. Irreversible damage can occur within 4 to 8 hours. The classic six P’s are pain, paresthesia, pallor, pulselessness, paralysis and poikilothermia, but they are not equally useful: the earliest and most reliable signs are pain out of proportion to the injury, pain that increases with passive stretch of the digits, and paresthesia. Pallor, pulselessness and paralysis are late — a palpable pulse does not rule out compartment syndrome. Nursing actions: stop, do not elevate the limb above heart level (that reduces arterial inflow — keep it at heart level), do not apply ice, loosen or ask for the cast to be bivalved or the dressing split, hold nothing back on reporting, and escalate immediately. Definitive care is fasciotomy; diagnostic compartment pressure above 30 mmHg or a delta pressure under 30 mmHg is the surgical threshold.
Other musculoskeletal red flags: fat embolism syndrome, typically 24–72 hours after a long bone or pelvic fracture, presenting as hypoxemia with new dyspnea, acute confusion, and a petechial rash across the chest, axillae and conjunctivae; cauda equina syndrome — saddle anesthesia, new urinary retention or incontinence, bilateral leg weakness and bowel dysfunction — a surgical emergency; suspected deep vein thrombosis with new unilateral calf swelling, warmth and pain (do not rely on Homans sign, which is neither sensitive nor specific); and a hip fracture presenting as a shortened, externally rotated leg in a patient who cannot bear weight after a fall.
Neurologic emergencies
For suspected stroke, use BE-FAST: Balance loss, Eyes (sudden vision change), Face droop, Arm drift, Speech difficulty, Time — establish and document the last known well time, which is the time the patient was last seen at neurologic baseline, not the time symptoms were discovered. Activate the stroke alert, keep the patient NPO until a swallow screen is passed, obtain a point-of-care glucose (hypoglycemia is the great stroke mimic), and get the patient to non-contrast CT. Standard targets are door-to-CT within 25 minutes and door-to-needle for thrombolysis within 60 minutes; IV thrombolysis is generally considered within 4.5 hours of last known well, and mechanical thrombectomy in selected patients up to 24 hours. Deficit severity is scored with the NIHSS, 0 to 42.
Rising intracranial pressure announces itself in level of consciousness first — restlessness, then confusion, then a falling GCS — followed by headache, vomiting, and pupillary changes (a sluggish then fixed, dilated pupil on the side of the lesion from third nerve compression). Cushing triad — rising systolic blood pressure with a widening pulse pressure, bradycardia, and irregular or slowed respirations — is a late sign of impending herniation, not an early warning. Normal pulse pressure is 30–40 mmHg; a pressure of 180/60 in a head-injured patient with a heart rate of 48 is an emergency call, not a documentation entry. Decorticate posturing (flexion toward the core) is bad; decerebrate posturing (extension) is worse; progression from one to the other is deterioration.
Autonomic dysreflexia occurs in patients with spinal cord injury at or above T6: a noxious stimulus below the level of injury triggers sudden severe hypertension (systolic often 20–40 mmHg above the patient’s baseline, sometimes far higher), a pounding headache, bradycardia, flushing and sweating above the lesion with pallor and cool skin below, nasal congestion and anxiety. Act in this order: sit the patient upright and lower the legs, loosen constrictive clothing and abdominal binders, then find and remove the trigger — a distended bladder or kinked catheter is the cause in the large majority, then fecal impaction, then skin pressure — while checking blood pressure every 2–5 minutes and calling for help. Untreated it causes stroke, seizure and death.
| Parameter | Adult expected | Across the lifespan |
|---|---|---|
| Heart rate | 60–100 beats/min | Newborn 100–180; infant 100–160; toddler 90–140; preschool 80–120; school-age 75–118; adolescent 60–100 |
| Respiratory rate | 12–20 breaths/min | Newborn 30–60; infant 30–53; toddler 22–37; preschool 20–28; school-age 18–25; adolescent 12–20 |
| Blood pressure | Less than 120/80 mmHg; pulse pressure 30–40 | Pediatric BP is percentile-based by age, sex and height; older adults commonly have wider pulse pressures from arterial stiffening |
| Temperature | 36.5–37.5 °C (97.7–99.5 °F) oral | Older adults run lower and may not mount a fever with infection; infants lose heat quickly |
| SpO2 | 95–100% on room air | Chronic lung disease targets are often 88–92% per order |
| Pupils | 2–5 mm, equal, round, briskly reactive | Smaller and more sluggish in older adults; up to 1 mm anisocoria may be physiologic if longstanding and reactive |
| GCS | 15 | Pediatric GCS uses age-appropriate verbal and motor responses |
Serial checks, charting and SBAR
Neurologic checks are ordered at a frequency (every 15 minutes, hourly, every 4 hours) because trend is the finding. Perform them the same way every time, at the same depth, using the same stimulus — otherwise the “change” you detect is your technique. A complete neuro check includes level of consciousness and orientation, GCS components, pupils (size in millimeters and reactivity, both eyes), motor strength in all four extremities, sensation, speech quality and vital signs.
| Vague entry | Precise entry a nurse can act on |
|---|---|
| “Neuro checks WNL. Pupils equal.” | “Alert and oriented ×4. GCS 15 (E4 V5 M6). Pupils 3 mm bilaterally, round, brisk to light, consensual intact. Strength 5/5 all four extremities, no pronator drift. Sensation intact to light touch all extremities. Speech clear, no aphasia or dysarthria. BP 128/74, HR 76, RR 16.” |
| “Patient more sleepy this shift, will monitor.” | “1400: GCS 11 (E3 V3 M5), down from 15 at 1200. Right pupil 5 mm sluggish, left 3 mm brisk. Left arm drift with 3/5 grip, right 5/5. BP 176/62 (pulse pressure 114, was 128/78), HR 52, RR 10 and irregular. Rapid response activated 1403, provider notified 1404.” |
| “Complains of cast pain, medicated.” | “2210: Right forearm pain 9/10, unrelieved 45 min after oxycodone 5 mg, described as deep and burning, markedly worse with passive finger extension. Fingers cool and dusky compared to left, cap refill 4 sec (left 2 sec), numbness in index and middle fingers, radial pulse palpable. Cast intact and snug. Limb kept at heart level, not elevated. Provider paged 2212.” |
When you escalate, use SBAR so the person on the other end of the phone gets what they need in fifteen seconds. Compartment syndrome example: S — “This is Jordan Ellis, RN, on 4 West. I’m calling about Mr. Alvarez in 412, post-op day one right radius ORIF with a long-arm cast. I am concerned about acute compartment syndrome.” B — “He fell yesterday, had a closed distal radius fracture repaired at 1500, has had a well-controlled pain score of 3 to 4 all evening.” A — “Since 2130 his pain is 9 out of 10, unrelieved by oxycodone, and severely worse with passive extension of his fingers. He has new numbness in the index and middle fingers, cap refill 4 seconds on the right versus 2 on the left, fingers cool and dusky. Radial pulse is still present. I have kept the arm at heart level and removed nothing.” R — “I need you to evaluate him now for compartment syndrome and give me an order to bivalve or remove the cast. Can you come to the bedside, or should I activate the rapid response team?”
Stroke example: S — “Room 216, Mrs. Chen, new left-sided weakness and slurred speech, I am calling a stroke alert.” B — “72-year-old admitted for pneumonia, atrial fibrillation, on apixaban, baseline oriented ×4 and independent.” A — “Last known well 1830 when I gave her medications. At 1905 she has left facial droop with forehead sparing, left arm drift with 2/5 grip, left leg 4/5, dysarthric speech, BE-FAST positive. Glucose 112. BP 168/88, HR 96 irregular. NPO, head of bed 30 degrees, IV patent.” R — “I need stat CT and the stroke team at the bedside now; please confirm the code stroke activation.”
Delegation and scope
The Five Rights of Delegation are right task, right circumstance, right person, right direction and communication, right supervision and evaluation. The rule that never bends: the RN may delegate a task, never the nursing process. Assessment, interpretation, teaching, evaluation, clinical judgment and any patient who is unstable or changing stay with the RN. A UAP may collect data and report it; only the RN may decide what it means.
| May be delegated to UAP | Stays with the RN (or LPN/LVN per state scope) |
|---|---|
| Ambulating a stable patient with a specified device and level of assistance | The initial and any ongoing musculoskeletal or neurologic assessment, including the first ambulation after a change in status |
| Performing taught passive or active-assist range of motion on a stable patient | Determining that range of motion is safe, and interpreting new pain or resistance during it |
| Applying an ordered immobilizer, splint or compression device that is already fitted | Neurovascular checks distal to a fracture, cast or surgical site — and the decision that a limb is compromised |
| Repositioning, transferring with a lift, applying a gait belt, sitting with a fall-risk patient | Fall-risk assessment and the plan of care that follows it; teaching the patient and family |
| Measuring and reporting vital signs and pulse oximetry on a stable patient | Neuro checks and GCS scoring, orthostatic vital signs on a symptomatic patient, and any vital sign on an unstable patient |
| Reporting exactly what was observed — “he could not lift his left arm during his bath” | Deciding what that observation means, escalating it, and documenting the assessment |
Pain out of proportion under a cast, a new focal deficit, a falling GCS with a widening pulse pressure, saddle anesthesia with retention, and severe hypertension with headache in a T6-or-above spinal cord injury are all escalations now — delivered in SBAR, by the RN, with a specific request attached.
The chapter in one breath
The musculoskeletal and neurologic exams are built the same way: inspect, palpate, percuss and auscultate — the sequence used in every region except the abdomen, where auscultation moves ahead of percussion and palpation so the bowel is heard before it is provoked — then, for joints, add active range of motion, passive range of motion and strength graded 0 to 5, always compared left to right. Range of motion is charted in degrees; effusion, warmth and crepitus are found with your hands; gait and the Timed Up and Go (12 seconds or more equals fall risk) tell you whether any of it works. On the neurologic side, level of consciousness comes first, scored as a GCS documented in its components, followed by orientation, delirium screening with the CAM, cranial nerves I to XII, motor tone and pronator drift, cerebellar coordination, sensation mapped to dermatomes, and reflexes graded 0 to 4+ with 2+ expected. The patterns then sort themselves into upper versus lower motor neuron. Findings only matter if they are trended and charted concretely and, when they are red flags — compartment syndrome, cauda equina, autonomic dysreflexia, stroke, rising intracranial pressure — escalated immediately in SBAR by the RN, who may delegate the task but never the assessment.
Words worth knowing
| Term | What it means |
|---|---|
| Active range of motion | Movement the patient produces themselves; tests joint, muscle, nerve and willingness together. |
| Passive range of motion | Movement you produce for a relaxed patient; isolates the joint itself. |
| Crepitus | Palpable or audible grating within a joint or under the skin during movement. |
| Bulge sign | Bedside maneuver that reveals a small knee effusion by milking fluid from one side of the patella to the other. |
| Antalgic gait | A limp in which the patient shortens time spent bearing weight on the painful limb. |
| Trendelenburg sign | Pelvic drop on the unsupported side during single-leg stance, indicating gluteus medius weakness on the standing side. |
| Timed Up and Go (TUG) | Rise, walk 10 feet, turn, return, sit; 12 seconds or more indicates increased fall risk. |
| Neurovascular check | Serial assessment distal to an injury or cast — colour, temperature, capillary refill, pulses, sensation, movement, pain and edema. |
| Compartment syndrome | Rising pressure inside a closed fascial space causing ischemia; earliest signs are pain out of proportion, pain on passive stretch and paresthesia. |
| Glasgow Coma Scale (GCS) | Standardized score of eye, verbal and motor response, 3 to 15; 8 or less signals inability to protect the airway. |
| Pronator drift | Downward drift and pronation of one outstretched arm with eyes closed — a sensitive sign of a contralateral corticospinal lesion. |
| Dysmetria | Overshooting or undershooting a target on finger-to-nose testing; a cerebellar sign. |
| Romberg test | Standing with feet together, eyes open then closed; increased sway with eyes closed indicates proprioceptive or vestibular dysfunction. |
| Babinski response | Great toe dorsiflexion with fanning on plantar stimulation; normal until about 2 years of age, an upper motor neuron sign after that. |
| Clonus | Rhythmic involuntary beats of plantar flexion after brisk dorsiflexion; sustained clonus is always abnormal. |
| Dermatome | The skin region supplied by a single spinal nerve root, used to localize sensory loss. |
| Aphasia | Loss of language — expressive (halting, effortful) or receptive (fluent but meaningless) — distinct from dysarthria, which is slurred articulation. |
| Cushing triad | Rising systolic pressure with widening pulse pressure, bradycardia and irregular respirations; a late sign of rising intracranial pressure. |
| Autonomic dysreflexia | Severe hypertension with headache and flushing above the lesion in spinal cord injury at or above T6, triggered by a noxious stimulus below it. |
| Cauda equina syndrome | Saddle anesthesia, urinary retention or incontinence and bilateral leg weakness from compression of the lumbosacral nerve roots; a surgical emergency. |