Reproductive
The reproductive systems bring their own set of disorders — hormonal, structural, infectious, and malignant. This chapter covers the common female and male conditions students meet on the floor, the cancers to screen for, and the sexually transmitted infections that quietly cause the most long-term harm.
By the end of this chapter you can
- Recognize common female disorders (PCOS, endometriosis, fibroids, PID).
- Name the female cancers and how cervical and breast cancer are screened.
- Explain BPH and tell it from prostate cancer.
- Identify testicular torsion as an emergency.
- Distinguish the major bacterial and viral STIs.
Section 1Female reproductive disorders
Every month, a healthy uterus rehearses for a pregnancy that usually does not come. This rehearsal is the menstrual cycle, and understanding its normal rhythm makes almost every female reproductive disorder easier to reason through. In the first half (the follicular phase), the pituitary releases FSH, an ovarian follicle matures, and rising estrogen thickens the uterine lining (the endometrium). A surge of LH triggers ovulation around day 14. The emptied follicle becomes the corpus luteum, which pumps out progesterone to hold the lining stable (the luteal phase). If no pregnancy implants, the corpus luteum dies, hormones fall, and the lining sheds as menstruation. Roughly a 28-day loop, though 21 to 35 days is often normal.
When the cycle misbehaves: menstrual disorders
Dysmenorrhea is painful periods. The primary type comes from excess prostaglandins, which cause the uterine muscle to cramp hard and briefly cut off its own blood supply (ischemia) - the same mechanism behind the crampy, labor-like pain. This is why NSAIDs, which block prostaglandin synthesis, work so well. Secondary dysmenorrhea points to an underlying problem like endometriosis or fibroids.
Amenorrhea means absent periods. Primary is never having started by around age 15; secondary is a loss of previously regular cycles for 3 or more months. Pregnancy is the most common cause of secondary amenorrhea and must be ruled out first, but stress, extreme exercise, low body weight, and thyroid or prolactin problems also silence the hypothalamic-pituitary-ovarian axis.
Abnormal uterine bleeding (AUB) covers bleeding that is too heavy (menorrhagia), too frequent, or between periods (metrorrhagia). Often it reflects anovulation: without ovulation there is no progesterone, so estrogen builds the lining unopposed until it outgrows its blood supply and sheds erratically. Chronic heavy loss commonly causes iron-deficiency anemia.
PCOS: the hormone-and-metabolism tangle
Polycystic ovary syndrome is the most common endocrine disorder in reproductive-age women. Think of three linked problems: irregular or absent cycles (from chronic anovulation), androgen excess (causing hirsutism, acne, and scalp thinning), and insulin resistance. The insulin piece is the engine that drives much of the rest: high insulin nudges the ovaries to make more androgens and lowers SHBG, freeing even more testosterone to circulate. The ovaries fill with many small immature follicles - the "polycystic" appearance on ultrasound. Because cycles do not complete, the lining sits under unopposed estrogen, raising the long-term risk of endometrial hyperplasia. PCOS also carries higher risk for type 2 diabetes and metabolic syndrome, which is why lifestyle change and sometimes metformin are frontline.
Endometriosis: the right tissue in the wrong place
In endometriosis, tissue that behaves like endometrium grows outside the uterus - on the ovaries, ligaments, and pelvic peritoneum. It still answers to the monthly hormone cues, so it thickens and bleeds with each cycle. But that blood has nowhere to drain. The result is chronic inflammation, scarring, and adhesions that glue pelvic organs together. Classic symptoms are cyclic pelvic pain that worsens with menses, dyspareunia (painful intercourse), and infertility. On the ovary, trapped old blood can form a "chocolate cyst" (endometrioma). Diagnosis is often confirmed by laparoscopy.
Fibroids and pelvic inflammatory disease
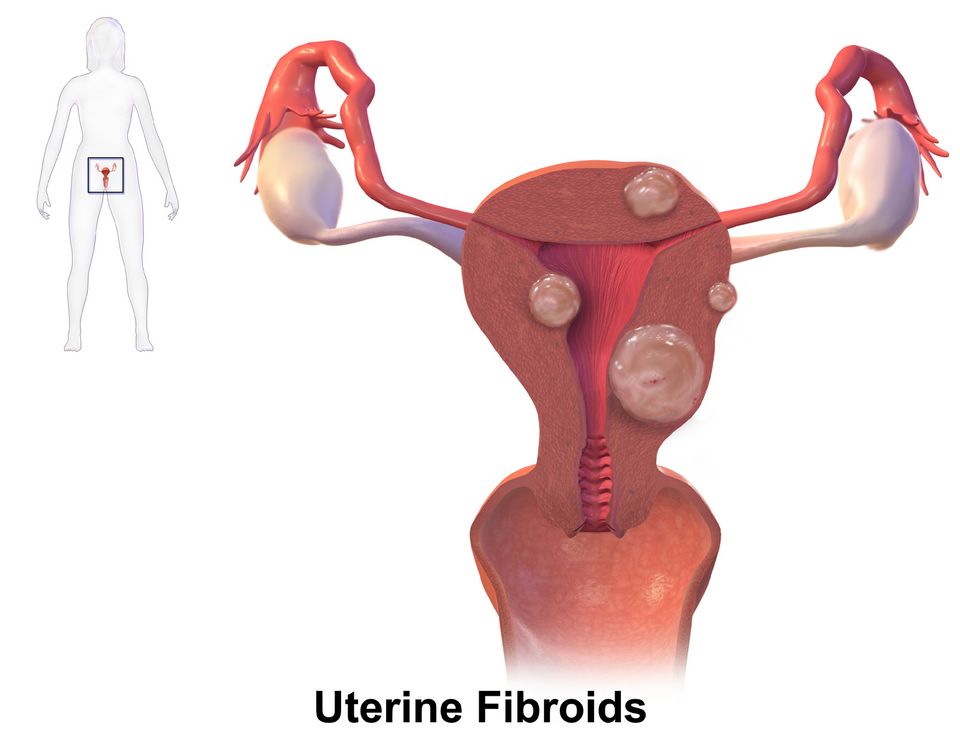
Uterine fibroids (leiomyomas) are benign smooth-muscle tumors of the uterine wall. They are estrogen-sensitive, so they tend to grow during reproductive years and shrink after menopause. Many are silent, but larger ones cause heavy or prolonged bleeding, pelvic pressure, and sometimes urinary frequency by pressing on the bladder.
Pelvic inflammatory disease (PID) is an ascending infection - usually Chlamydia or gonorrhea - that climbs from the cervix up into the uterus, tubes, and ovaries. The inflammation scars the fallopian tubes, which is why PID is a leading cause of ectopic pregnancy and infertility. Watch for lower abdominal pain, fever, discharge, and cervical motion tenderness.
| Feature | Endometriosis | Uterine fibroids |
|---|---|---|
| Nature | Endometrial-type tissue outside the uterus | Benign smooth-muscle tumor in the uterine wall |
| Hallmark pain | Cyclic pain, dyspareunia | Pressure, heaviness; often painless |
| Bleeding | Variable | Heavy or prolonged menses |
| Fertility impact | Common (adhesions) | Depends on size and location |
You can explore these disorders side by side in the interactive figure below.
- The cycle runs on FSH/LH driving estrogen (builds the lining) then progesterone (stabilizes it); when ovulation fails, unopposed estrogen causes abnormal bleeding and raises endometrial cancer risk.
- Primary dysmenorrhea is prostaglandin-driven uterine ischemia (NSAIDs help); rule out pregnancy first in secondary amenorrhea.
- PCOS links anovulation, androgen excess, and insulin resistance - insulin resistance often drives the androgen excess.
- Endometriosis is uterine-type tissue outside the uterus causing cyclic pain, adhesions, and infertility; fibroids are estrogen-sensitive benign muscle tumors causing heavy bleeding and pressure.
- PID is an ascending STI-related infection that scars the tubes, raising the risk of ectopic pregnancy and infertility.
Section 2Cancers of the female system

Every month during the reproductive years, the ovaries release estrogen and progesterone in a carefully timed rhythm. Estrogen tells the endometrium (the uterine lining) to grow and thicken; progesterone, released after ovulation, matures that lining and then allows it to shed as a period. The cervix (the neck of the uterus) is lined by fast-turnover cells where two tissue types meet, and the breast is made of milk-making glands and ducts that respond to those same hormones. Cancer arises when the normal instructions for cell growth get corrupted and cells divide without a stop signal. Here is where that goes wrong in the female reproductive system, and why each one behaves the way it does.
Cervical cancer: a virus you can vaccinate against
Nearly all cervical cancer starts with human papillomavirus (HPV), a common sexually transmitted virus. High-risk strains (especially types 16 and 18) slip proteins into cervical cells that switch off the body's tumor-suppressor genes, so damaged cells keep dividing instead of self-destructing. This usually happens slowly: normal cells become dysplasia (pre-cancer), and only years later become invasive cancer. That slow lag is exactly what makes cervical cancer so preventable. A Pap smear scrapes cells from the cervix to catch dysplasia before it turns malignant, and HPV co-testing looks for the virus itself. The HPV vaccine (given ideally around ages 11 to 12, before exposure) blocks infection in the first place. Early cervical cancer is often silent; a classic later warning sign is postcoital bleeding (bleeding after intercourse) or abnormal spotting.
Endometrial (uterine) cancer: too much estrogen, unopposed
Estrogen builds the endometrium; progesterone keeps that growth in check and triggers shedding. When estrogen acts without enough progesterone to balance it, the lining keeps thickening. This is called unopposed estrogen, and over time it drives endometrial hyperplasia, which can progress to cancer. This explains the risk factors: obesity (fat tissue makes extra estrogen), never having been pregnant, early menarche and late menopause (more lifetime estrogen), PCOS, and taking estrogen therapy without progesterone. The good news is that this cancer usually announces itself early with postmenopausal bleeding or abnormal uterine bleeding. Any bleeding after menopause is endometrial cancer until proven otherwise and warrants prompt evaluation.
Ovarian cancer: the quiet one
The ovaries sit deep in the pelvis with room to grow unnoticed, so ovarian cancer often causes no clear symptoms until it has spread. When symptoms do appear they are vague and easy to dismiss: bloating, early satiety (feeling full quickly), pelvic or abdominal discomfort, and urinary urgency. Because there is no reliable screening test for average-risk women, it is frequently found late, which is why it carries a high mortality. Risk rises with BRCA1/BRCA2 gene mutations, family history, nulliparity, and more lifetime ovulations - the "incessant ovulation" idea, which is why pregnancy, breastfeeding, and combined oral contraceptives all lower the risk by giving the ovary a rest. Note that this is the mirror image of endometrial cancer: ovulating produces a corpus luteum and therefore progesterone, which protects the endometrium, so endometrial risk climbs with anovulation and unopposed estrogen instead. The two cancers share nulliparity as a risk factor, but for opposite ovulatory reasons. Nurses play a real role here by taking persistent, new bloating or fullness seriously rather than brushing it off.
Breast cancer: risk, warning signs, and screening
Breast tissue is estrogen-responsive, so most risk factors trace back to lifetime estrogen exposure and genetics: early menarche, late menopause, never breastfeeding, older age, and inherited BRCA1/BRCA2 mutations (which sharply raise both breast and ovarian risk). Warning signs come from a growing mass distorting normal tissue: a hard, fixed, painless lump, skin dimpling or a peau d'orange (orange-peel) texture, nipple retraction, or bloody nipple discharge. Screening mammography (usually starting around age 40 to 50 and continuing regularly) catches tumors before they can be felt.
| Feature | Cervical | Endometrial |
|---|---|---|
| Main driver | HPV infection | Unopposed estrogen |
| Key prevention/screen | Pap smear, HPV vaccine | Watch for abnormal bleeding |
| Classic warning sign | Postcoital bleeding | Postmenopausal bleeding |
| Detected | Often early (screenable) | Often early (bleeds) |
Notice the pattern: cancers that bleed or can be screened tend to be caught early, while the quiet ovaries are caught late. That single idea organizes most of what you need to remember.
- Cervical cancer is caused by HPV; the Pap smear catches pre-cancer and the HPV vaccine prevents infection, making it highly preventable.
- Endometrial cancer is driven by unopposed estrogen; obesity, nulliparity, and estrogen-only therapy raise risk, and postmenopausal bleeding is the key early sign.
- Ovarian cancer is the quiet one, usually found late with vague bloating and fullness because there is no reliable screening test; risk rises with BRCA1/BRCA2, family history, nulliparity, and more lifetime ovulations, so pregnancy, breastfeeding, and combined oral contraceptives are protective.
- Breast cancer risk rises with estrogen exposure and BRCA1/BRCA2; watch for a hard fixed lump, skin dimpling, or nipple changes, and screen with mammography.
- Any postmenopausal bleeding is cancer until proven otherwise and needs prompt evaluation.
Section 3Male reproductive disorders
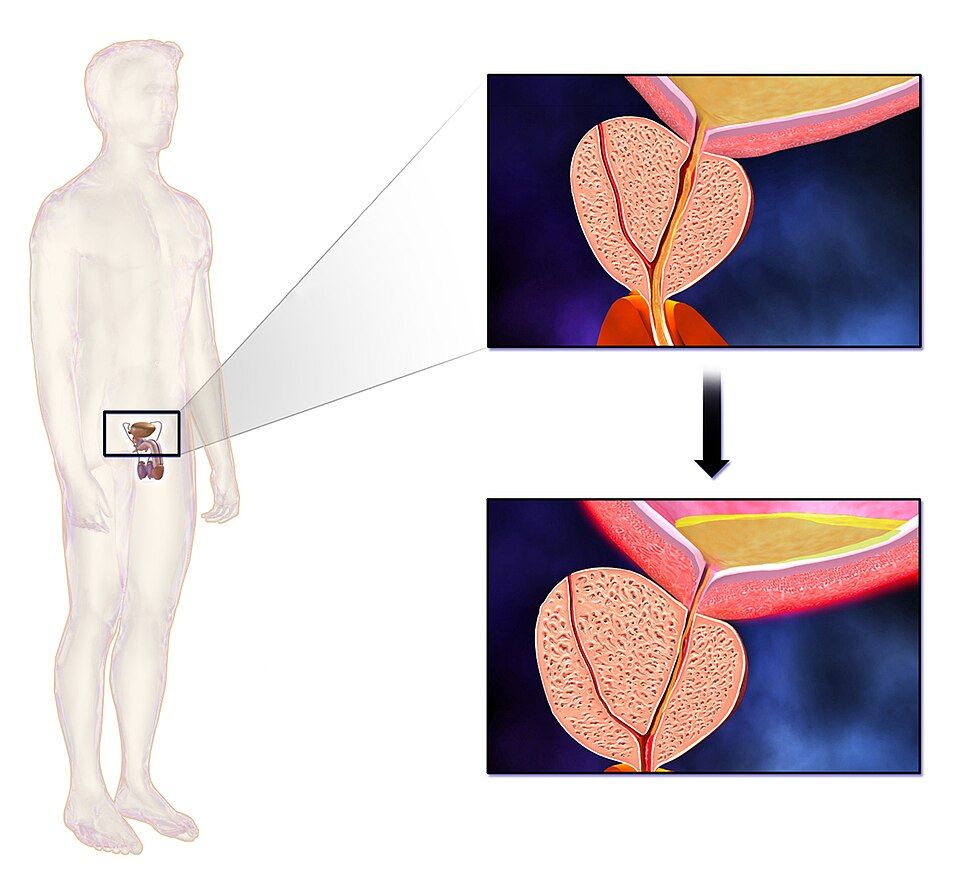
The male reproductive system is built around a simple plumbing problem: the same tube, the urethra, has to carry both urine out of the bladder and semen out during ejaculation. That urethra runs straight through the middle of the prostate, a walnut-sized gland that sits just below the bladder and adds fluid to semen. Blood flow matters too: an erection is really a vascular event, where arteries relax and let blood pool inside the penis. Keep those two ideas in mind, the tube running through the prostate and the blood-flow story, and most male reproductive disorders start to make sense.
Benign prostatic hyperplasia (BPH)
BPH is exactly what the name says: benign (not cancer), hyperplasia (too many cells). With age and lifelong androgen (mostly DHT, dihydrotestosterone) exposure, the prostate slowly enlarges. Because the urethra passes right through the gland, that growth squeezes the tube like a hand gently closing around a straw. Everything downstream flows from that pinch. The stream gets weak and hesitant because it is harder to push urine past the narrowing. The bladder muscle (detrusor) has to work harder, so it thickens and becomes irritable, which drives urinary frequency, urgency, and nocturia (waking at night to void). Over time the bladder cannot fully empty, leaving residual urine, and in the worst case flow stops completely, called acute urinary retention. These lower urinary tract symptoms are often lumped as LUTS.
Prostatitis
Prostatitis is inflammation of that same gland, and it feels very different from BPH. Acute bacterial prostatitis is usually caused by gut or urinary organisms (often E. coli) tracking into the prostate. Because it is an active infection, the man is genuinely sick: fever, chills, malaise, plus pelvic or perineal pain and painful, difficult urination (dysuria). On exam the prostate is boggy, swollen, and exquisitely tender. Chronic prostatitis is the slow-burn version, with lingering pelvic discomfort and recurrent urinary infections but few systemic signs.
| Feature | BPH | Acute prostatitis |
|---|---|---|
| Cause | Age-related growth (androgen-driven) | Bacterial infection |
| Fever / feeling sick | No | Yes, often high |
| Onset | Gradual, over years | Sudden, over hours to days |
| Prostate on exam | Enlarged, smooth, firm | Swollen, boggy, very tender |
| Main problem | Obstructed flow | Infection plus dysuria |
Erectile dysfunction (ED)
Erectile dysfunction is the consistent inability to get or keep an erection firm enough for intercourse. Since an erection depends on arteries dilating and filling the penis with blood, ED is most often a vascular problem. The same processes that clog coronary arteries, atherosclerosis, diabetes, hypertension, and smoking, also damage the small penile vessels and the endothelium that releases nitric oxide, the signal that tells smooth muscle to relax. This is why ED is often called an early warning sign: those small vessels narrow before the big ones cause a heart attack. Nerve damage (as in diabetes or after prostate surgery), low testosterone, certain medications, and psychological factors add to the picture.
Testicular torsion
Testicular torsion is a true surgical emergency. The testicle twists on its spermatic cord, kinking the blood supply exactly like stepping on a garden hose. Without arterial flow the testicle becomes ischemic and, if not fixed quickly, dies. It classically strikes adolescents with sudden, severe one-sided scrotal pain, often with nausea and vomiting. The affected testicle may sit high and horizontal, and the cremasteric reflex (stroking the inner thigh normally lifts the testicle) is typically absent. Time is the whole story: salvage rates are best within about 6 hours, so torsion goes straight to surgery, and often it is not imaged first if the diagnosis is clear.
Explore the interactive figure below to see how each of these disorders maps onto male reproductive anatomy.
- BPH is benign, age-related prostate growth that squeezes the urethra, causing weak stream, frequency, nocturia, and possible retention.
- Prostatitis is inflammation of the prostate; the acute bacterial form brings fever, pelvic pain, and a boggy, tender gland, unlike the painless enlargement of BPH.
- Erectile dysfunction is usually vascular and can be an early warning sign of underlying cardiovascular disease like atherosclerosis or diabetes.
- Testicular torsion is a surgical emergency: sudden severe scrotal pain with an absent cremasteric reflex, best salvaged within about 6 hours.
- Because the urethra runs through the prostate, most prostate disorders show up first as changes in the urinary stream.
Section 4Cancers of the male system
The male reproductive system runs on two organs that quietly do very different jobs. The testes sit outside the body in the scrotum, where the slightly cooler temperature lets them make sperm and pump out testosterone. The prostate is a walnut-sized gland wrapped around the urethra just below the bladder; its job is to add fluid to semen. Because the prostate hugs the urine tube, anything that makes it swell can squeeze that tube and change how a man pees. Keep that anatomy in mind, because it explains almost every symptom in this section.
Prostate cancer: common and often patient
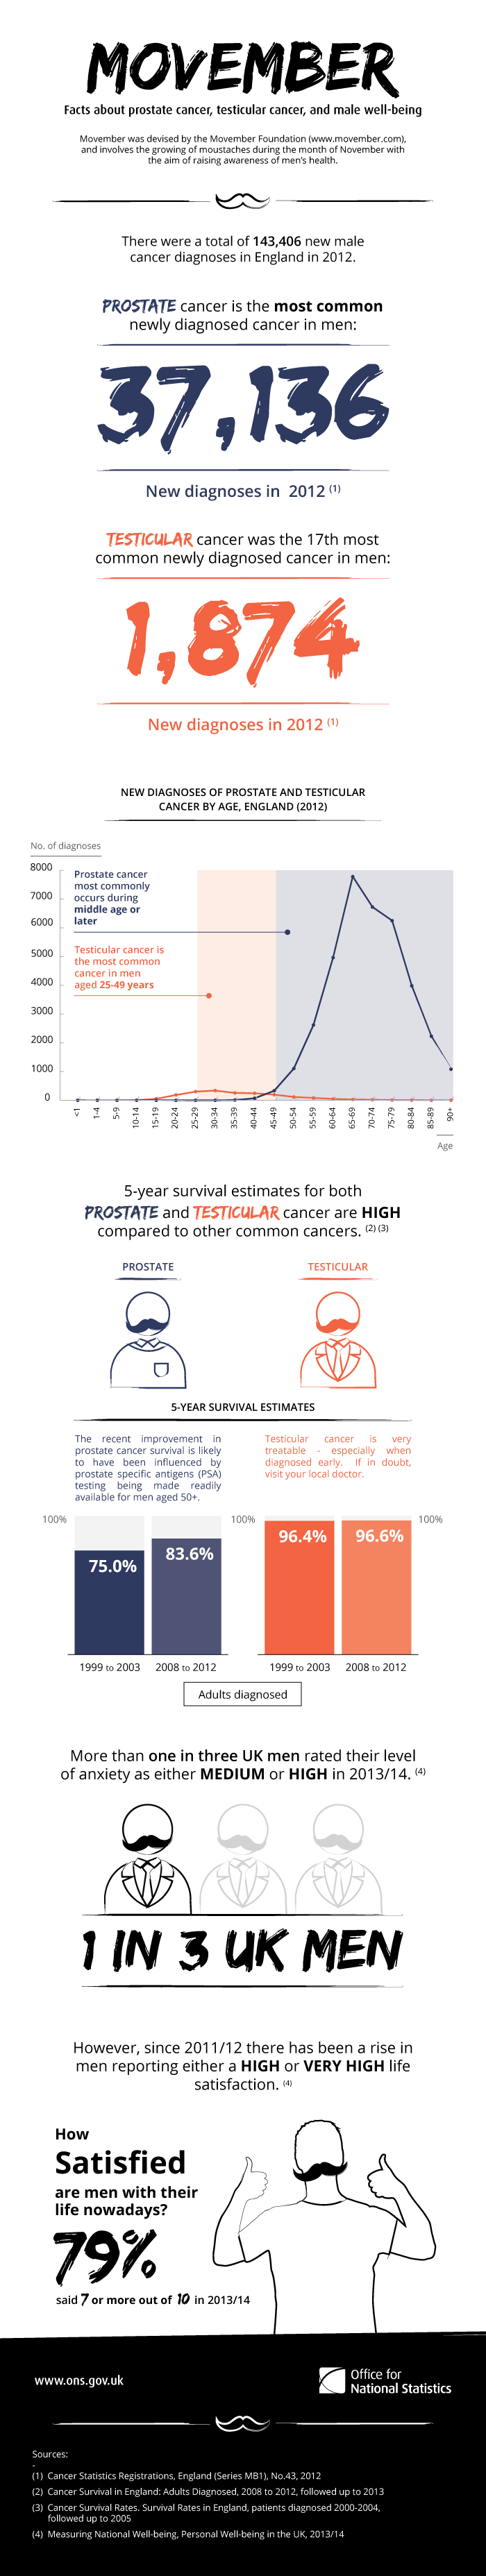
Prostate cancer is the most common non-skin cancer in men, and the risk climbs steeply with age, especially after 65. It is also frequently slow-growing, so many men live for years with disease that never threatens them. The tumor usually starts in the peripheral (outer) zone of the gland, which is why it often causes no early symptoms at all, and why a clinician can sometimes feel a hard, irregular nodule on a digital rectal exam (DRE). Screening pairs the DRE with a blood test for PSA (prostate-specific antigen), a protein the prostate normally leaks in small amounts. When cancer cells disrupt the gland's architecture, more PSA escapes into the blood, so a rising level is a red flag, though not a diagnosis. Because prostate cancer likes to spread to bone, a later sign can be deep, unexplained back or hip pain.
Cancer versus BPH: same gland, different problem
Students mix these up constantly because both make the prostate bigger and both mess with urination. The key difference is where and what kind. Benign prostatic hyperplasia (BPH) is non-cancerous overgrowth of the inner (transitional) zone, the part closest to the urethra, so it squeezes the tube early and loudly. Cancer usually grows in the outer zone, so it stays quiet until it is more advanced.
| Feature | BPH (benign) | Prostate cancer |
|---|---|---|
| Nature | Overgrowth of normal cells | Malignant cells that can spread |
| Usual zone | Inner/transitional (near urethra) | Peripheral/outer |
| Early urinary symptoms | Common and prominent | Often none until advanced |
| DRE finding | Smooth, rubbery, symmetric | Hard, irregular nodule |
| PSA | Mildly elevated | Often higher or rising |
The urinary symptoms of BPH follow directly from the squeezed urethra: a weak stream, hesitancy (waiting for flow to start), dribbling, and nocturia (waking to pee) because the bladder never fully empties. These same symptoms can appear in advanced cancer, so symptoms alone cannot tell the two apart. That is exactly why the exam and PSA matter.
Testicular cancer: the young man's cancer
Testicular cancer flips the age script. It is the most common solid cancer in men roughly 15 to 35 years old, and the biggest risk factor is a history of an undescended testicle (cryptorchidism), even one surgically corrected in childhood. The classic presentation is a painless, firm lump or swelling in one testicle, often found by chance or during a shower. Because it is painless, men easily ignore it, which is dangerous because these tumors can grow quickly. Many arise from germ cells and can raise tumor markers such as AFP, beta-hCG, and LDH, which help with diagnosis and tracking. The reassuring news is that testicular cancer is highly treatable, with excellent cure rates even when it has spread, so early detection changes outcomes dramatically.
When to worry and refer
Refer promptly for evaluation when you see a hard or nodular prostate on exam, a rising or clearly elevated PSA, or new bone pain with a prostate history. For testes, any painless testicular mass, new firmness, or size change warrants urgent workup, usually a scrotal ultrasound, before assuming it is benign. Red flags such as blood in the urine or semen, unexplained weight loss, or difficulty urinating also deserve escalation. Your nursing role is not to diagnose but to notice, document, and route, and to normalize screening so men actually show up.
- Prostate cancer is common, often slow-growing, favors older men, grows in the gland's outer zone, and is screened with PSA plus digital rectal exam.
- BPH is benign inner-zone overgrowth that squeezes the urethra early (weak stream, hesitancy, nocturia); cancer stays outer and quiet until advanced, so exam and PSA distinguish them.
- PSA is a clue, not a diagnosis; infection, BPH, and recent exam can raise it, and a rising level earns a referral.
- Testicular cancer strikes young men (usually 15 to 35), typically a painless firm mass, and is highly curable, so monthly self-exam and early reporting matter.
- Refer promptly for a hard or nodular prostate, rising PSA, new bone pain, or any painless testicular mass.
Section 5Sexually transmitted infections

The reproductive tract has built-in defenses. The vagina keeps an acidic pH thanks to lactobacilli, cervical mucus forms a physical plug, and the mucosal lining of the urethra, cervix, and rectum is coated in immune cells ready to trap invaders. Sexually transmitted infections (STIs) happen when a pathogen — bacterial, viral, or protozoal — is passed through vaginal, anal, or oral contact and gets past those defenses to colonize mucosa or enter the bloodstream. The tricky part for nursing care is that many STIs are silent: the person feels fine while the organism quietly climbs the tract or spreads systemically.
Bacterial STIs: chlamydia and gonorrhea
Chlamydia trachomatis and Neisseria gonorrhoeae are the two most commonly reported bacterial STIs, and they often travel together. Both infect columnar epithelial cells of the cervix and urethra. When symptoms do appear, expect dysuria, mucopurulent discharge, or post-coital bleeding — but roughly 70% of women and many men have no symptoms at all, which is exactly why they spread. That silence is dangerous. If the organism ascends from the cervix into the uterus and fallopian tubes, it triggers pelvic inflammatory disease (PID). The resulting inflammation and scarring of the tubes can block egg transport, causing infertility and raising the risk of a life-threatening ectopic pregnancy. Gonorrhea can also disseminate into blood and joints (disseminated gonococcal infection). Both are treatable with antibiotics — chlamydia with doxycycline, gonorrhea with ceftriaxone — but treatment does not reverse scarring already done.
Syphilis and its stages
Syphilis, caused by the spirochete Treponema pallidum, is the great imitator because it moves through the body in distinct stages, each with different signs as the organism spreads from local tissue to the bloodstream and eventually the nervous system.
| Stage | What you see | Why |
|---|---|---|
| Primary | Single painless chancre at entry site; heals on its own | Local spirochete replication; often missed because it does not hurt |
| Secondary | Diffuse rash (often palms/soles), fever, lymphadenopathy | Organism has spread through blood, provoking a systemic immune response |
| Latent | No symptoms; positive serology | Bacteria persist quietly; still transmissible early on |
| Tertiary | Gummas, cardiovascular damage, neurosyphilis | Years of unchecked tissue and vessel destruction |
Penicillin remains the treatment. The painless, self-healing early lesions are exactly why untreated syphilis marches forward — the patient assumes it is gone.
Viral STIs
Viral STIs differ in a key way: antibiotics do nothing, and several are lifelong because the virus integrates into or hides within host cells.
- Human papillomavirus (HPV) — infects squamous epithelium. Low-risk strains cause genital warts; high-risk strains (16, 18) drive cervical, anal, and oropharyngeal cancers by disrupting tumor-suppressor genes. The HPV vaccine prevents the high-risk strains, and Pap/HPV screening catches precancerous change early.
- Herpes simplex virus (HSV) — causes painful vesicular genital lesions, then retreats into sacral nerve ganglia where it stays for life, reactivating under stress. Antivirals (acyclovir) suppress outbreaks but do not cure.
- HIV — attacks CD4 T-helper cells, progressively crippling immunity until opportunistic infections define AIDS. Modern antiretroviral therapy lets people live long lives and, when viral load is undetectable, prevents transmission.
- Hepatitis B — a bloodborne and sexually transmitted virus that inflames the liver and can cause chronic hepatitis, cirrhosis, and liver cancer. It is vaccine-preventable.
Why screening and prevention matter
Because so many STIs are asymptomatic, screening finds them before complications set in, and treating partners breaks the reinfection loop. Prevention layers together: barrier methods (condoms) reduce transmission, vaccines stop HPV and hepatitis B before exposure, and prompt treatment shortens the window of infectivity. For nurses, patient teaching is nonjudgmental, practical, and centered on the truth that catching an STI early is almost always easier than treating what it becomes.
- Chlamydia and gonorrhea are often silent but can ascend to cause PID, infertility, and ectopic pregnancy; treat the patient and partners.
- Syphilis progresses through primary (painless chancre), secondary (systemic rash), latent, and tertiary (neurosyphilis, cardiovascular) stages; penicillin treats it.
- Viral STIs (HPV, HSV, HIV, hepatitis B) resist antibiotics and are often lifelong; HPV and hepatitis B are vaccine-preventable.
- High-risk HPV drives cervical and other cancers; HIV destroys CD4 cells and immunity.
- Screening, partner treatment, barrier methods, and vaccination prevent the severe long-term complications of untreated STIs.
The chapter in one breath
- Endometriosis is ectopic endometrial tissue that still bleeds each cycle, causing chronic pelvic pain, dysmenorrhea, and infertility from adhesions and scarring.
- PID (usually ascending chlamydia or gonorrhea) inflames the upper tract, and its scarring is a leading cause of ectopic pregnancy and infertility.
- Cervical cancer is nearly always caused by persistent high-risk HPV (types 16 and 18), which is why HPV vaccination and Pap/HPV co-testing screening catch it early.
- Breast cancer risk climbs with lifetime estrogen exposure and BRCA1/BRCA2 mutations, and a new painless hard fixed lump or nipple change warrants mammography.
- BPH is a non-malignant enlargement of the prostate's inner zone that squeezes the urethra, causing hesitancy, weak stream, nocturia, and urinary retention.
- Prostate cancer usually arises in the peripheral zone (so it is felt on DRE and rarely obstructs early), often silent until an elevated PSA or bone metastases appear.
- Testicular cancer is the most common solid tumor in young men aged 15 to 35 and typically presents as a painless firm testicular lump.
- STIs often hide silently: chlamydia and gonorrhea may be asymptomatic yet cause PID and infertility, while untreated syphilis progresses through primary chancre, secondary rash, and tertiary organ damage.
ReferenceWords worth knowing
A quick reference for the terms in this chapter — skim it now, or circle back whenever a word trips you up.
- Amenorrhea
- The absence of menstrual periods, either because they never started by the expected age (primary) or because they stopped for three or more cycles in someone who previously menstruated (secondary), often signaling pregnancy, hormonal imbalance, or excessive stress or exercise.
- Benign prostatic hyperplasia (BPH)
- A non-cancerous enlargement of the prostate gland common in aging men that squeezes the urethra and causes urinary symptoms like weak stream, hesitancy, frequency, and nighttime urination (nocturia).
- BRCA
- The BRCA1 and BRCA2 tumor-suppressor genes whose inherited mutations sharply raise a person's lifetime risk of breast and ovarian (and some prostate) cancers because the damaged gene can no longer help repair DNA.
- Chlamydia
- A very common bacterial sexually transmitted infection caused by Chlamydia trachomatis that is often silent (asymptomatic) yet can quietly scar the reproductive tract and lead to pelvic inflammatory disease and infertility if untreated.
- Dysmenorrhea
- Painful menstrual cramping caused mainly by prostaglandin-driven uterine contractions, ranging from primary (no underlying disease) to secondary (from conditions like endometriosis or fibroids).
- Endometriosis
- A condition in which tissue resembling the uterine lining grows outside the uterus, bleeding cyclically with each period to cause chronic pelvic pain, painful intercourse, and often infertility.
- Fibroid
- A benign (non-cancerous) tumor of uterine smooth muscle, also called a leiomyoma, that can enlarge the uterus and cause heavy menstrual bleeding, pelvic pressure, and pain.
- Gonorrhea
- A bacterial sexually transmitted infection caused by Neisseria gonorrhoeae that inflames the urethra, cervix, or other mucous membranes and, if untreated, can spread to cause pelvic inflammatory disease or disseminated infection.
- HPV (human papillomavirus)
- A very common sexually transmitted virus whose high-risk strains can cause cervical, anal, and other cancers, while low-risk strains cause genital warts.
- HPV vaccine
- A vaccine (such as Gardasil) that protects against the high-risk human papillomavirus strains most likely to cause cervical and other cancers, given ideally before a person becomes sexually active.
- Pap smear
- A screening test that samples cells from the cervix to detect precancerous or cancerous changes early, often paired with HPV testing to catch problems before they become cancer.
- Pelvic inflammatory disease (PID)
- An infection of the upper female reproductive organs (uterus, fallopian tubes, ovaries), usually spreading upward from an untreated STI like chlamydia or gonorrhea, that can scar the tubes and cause infertility or ectopic pregnancy.
- Polycystic ovary syndrome (PCOS)
- A common hormonal disorder marked by irregular or absent ovulation, elevated androgens (causing acne and excess hair growth), and often insulin resistance, frequently seen with multiple small ovarian follicles on ultrasound.
- PSA (prostate-specific antigen)
- A protein made by the prostate and measured in the blood as a screening marker; higher levels can suggest prostate cancer but also rise with benign prostatic hyperplasia, infection, or inflammation.
- Syphilis
- A sexually transmitted infection caused by the bacterium Treponema pallidum that progresses in stages, starting with a painless sore (chancre) and, if untreated, eventually damaging the heart, brain, and other organs.
- Testicular torsion
- A surgical emergency in which the testicle twists on its spermatic cord, cutting off blood flow and causing sudden severe scrotal pain and swelling that must be relieved within hours to save the testicle.
DrillFlashcards for this unit
These are the Week 12 cards — the same deck as the hub, pulled in here so you can review the moment you finish reading. Tap the card to flip it; hit Shuffle to mix them up. To grade yourself and track mastery across the whole deck, open the full flashcards page.