States of Consciousness
Right now you are aware — of these words, of the chair beneath you, perhaps of a background hum you had tuned out until this sentence pointed to it. That awareness is consciousness, and it is not a single fixed thing but a moving landscape that shifts every day from alert wakefulness through drowsiness, sleep, and dreams, and that people deliberately alter with everything from coffee to anesthesia. This chapter follows consciousness across the twenty-four-hour cycle: the internal clock that drives it, the architecture of a night's sleep, the strange theater of dreaming, the disorders that disrupt it, and the drugs that hijack it. Understanding these states matters because roughly a third of your life is spent asleep — and what happens there shapes the memory, mood, and health of the two-thirds you spend awake.
By the end of this chapter you can
- Define consciousness and describe how awareness varies along a continuum.
- Explain what a biological rhythm is and identify the circadian rhythm as the body's daily clock.
- Describe how the suprachiasmatic nucleus, light, and melatonin regulate the sleep–wake cycle.
- Summarize the major theories of why we sleep.
- Distinguish the stages of NREM sleep from REM sleep by their brain waves, and describe how sleep cycles across a night.
- Compare theories of dreaming, including Freud's and the activation-synthesis hypothesis.
- Recognize the major sleep disorders — insomnia, sleep apnea, narcolepsy, and the parasomnias.
- Classify psychoactive drugs as depressants, stimulants, opioids, or hallucinogens, and explain tolerance and dependence.
Section 1What consciousness is
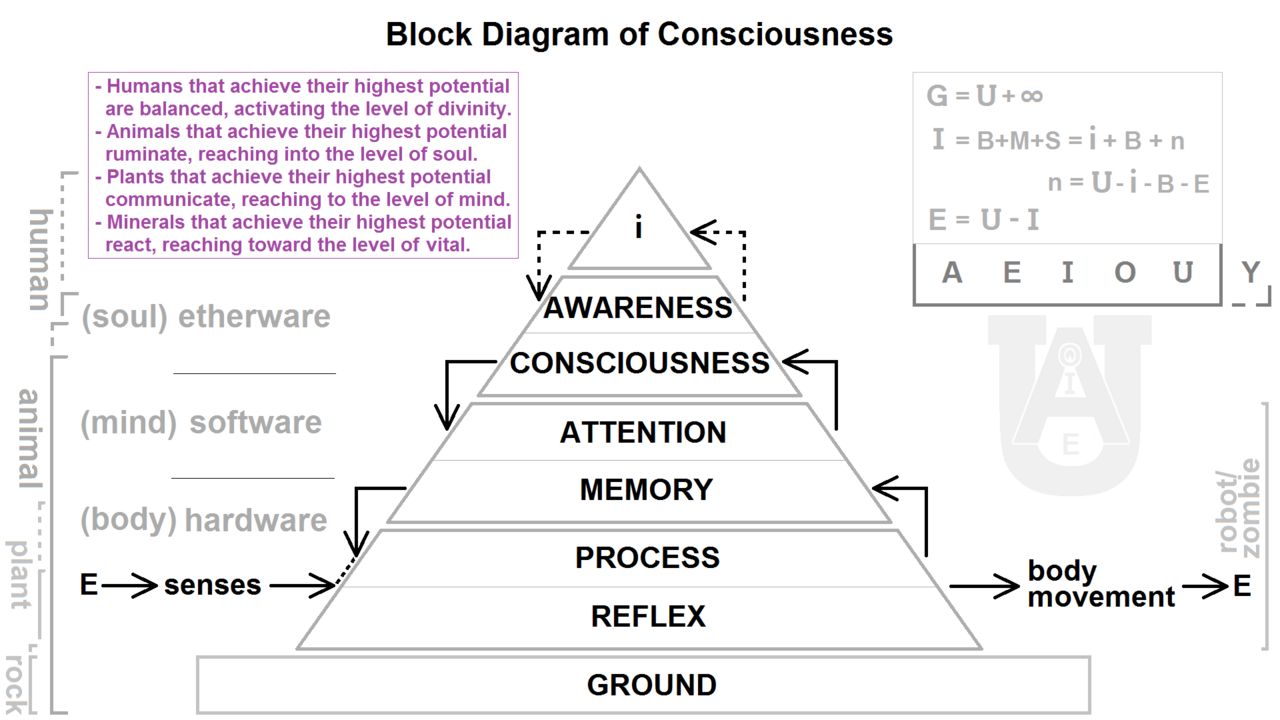
Awareness: the feature that defines consciousness
Psychologists define consciousness as your awareness of internal states and the external environment. The internal part includes your thoughts, your emotions, and body signals like hunger or pain; the external part includes everything your senses pick up from the world. Consciousness is famously hard to study because it is private — no one can directly observe your experience — yet it is the very thing psychology most wants to explain. For most of the twentieth century, behaviorists set it aside as untestable; today, tools like the EEG and functional brain imaging let researchers link states of awareness to measurable patterns of brain activity.
Consciousness is a continuum, not a switch
It is tempting to think of yourself as simply "awake" or "unconscious," but awareness comes in shades. At one end is sharp, effortful attention — the controlled processing you use to learn a new skill. At the other end is automatic processing, the low-awareness autopilot that lets an experienced driver navigate home while deep in conversation, remembering almost nothing of the route. Sleep lowers awareness further without switching it off entirely, and anesthesia or a coma lowers it further still. Even selective attention — the cocktail-party ability to focus on one voice in a noisy room — shows that consciousness is a spotlight of limited width, not a floodlight that captures everything at once.
Biological rhythms: the body runs on clocks
Much of the daily rise and fall of consciousness is driven by biological rhythms, recurring cycles of physiological activity built into the body. They are sorted by how long one cycle lasts. A circadian rhythm repeats roughly every twenty-four hours and governs the sleep–wake cycle, body temperature, and hormone release. An ultradian rhythm repeats more than once a day — the ninety-minute cycle that structures a night's sleep is the classic example. An infradian rhythm stretches longer than a day, as in the roughly twenty-eight-day menstrual cycle or seasonal shifts in mood. These clocks run whether or not you attend to them, which is why you grow sleepy at a predictable hour even on a day with no schedule.
| Rhythm | Cycle length | Examples in the body |
|---|---|---|
| Circadian | About 24 hours | Sleep–wake cycle, body temperature, cortisol and melatonin release, daily alertness |
| Ultradian | Shorter than 24 hours | The ~90-minute sleep cycle; cycles of hunger and focus across the day |
| Infradian | Longer than 24 hours | The menstrual cycle (~28 days); seasonal patterns of mood and behavior |
- Consciousness is awareness of internal states and the external environment.
- Awareness is a continuum — from controlled attention through automatic processing, sleep, and anesthesia — not an on/off switch.
- Biological rhythms are built-in cycles: circadian (~24 h), ultradian (<24 h), and infradian (>24 h).
- The circadian rhythm is the body's daily clock and the engine behind the sleep–wake cycle.
Section 2Sleep and the circadian rhythm

The sleep–wake cycle and the master clock
The body's twenty-four-hour clock is not a metaphor — it is a specific cluster of neurons called the suprachiasmatic nucleus (SCN), sitting in the hypothalamus just above where the optic nerves cross. The SCN keeps its own near-24-hour beat even in constant darkness, but it stays synchronized to the outside world through light. Special cells in the retina report how bright it is straight to the SCN, which then coordinates the daily rise and fall of alertness, body temperature, and hormones. Cues that reset this clock — chiefly light, but also meal times and activity — are called zeitgebers, German for "time-givers." When you fly across time zones, the SCN is briefly out of step with the local light schedule, and the grogginess and broken sleep of jet lag is the clock catching up.
Melatonin: the darkness hormone
The SCN does much of its work through a small endocrine gland called the pineal gland, which secretes the hormone melatonin. Melatonin is the body's chemical signal for "night": levels climb in the evening as light fades, peak in the small hours, and fall toward morning, nudging you toward sleep and helping keep you there. Because light suppresses melatonin, the timing of light exposure is powerful — bright morning light advances the clock and sharpens daytime alertness, while bright light late at night pushes the clock later and delays sleep. This is the mechanism behind one of the most common modern complaints about sleep, and behind the appeal of melatonin as an over-the-counter aid for jet lag and shift work.
Why do we sleep?
If sleep were not doing something essential, evolution would likely have discarded a state that leaves an animal defenseless for hours a day. Three complementary theories explain the pressure to sleep. The restorative theory holds that sleep repairs the body and brain: growth hormone is released, tissues rebuild, and a plumbing system called the glymphatic pathway flushes out metabolic waste, including proteins linked to brain disease. The adaptive (evolutionary) theory argues that sleep evolved to conserve energy and keep animals safely inactive during the hours when foraging would be dangerous. The memory-consolidation theory holds that sleep sorts, strengthens, and stores the day's learning — which is why pulling an all-nighter before an exam so reliably backfires.
| Theory | Core idea | Supporting evidence |
|---|---|---|
| Restorative | Sleep repairs body and brain and clears metabolic waste | Growth-hormone release, tissue repair, and glymphatic "wash-out" of waste peak during deep sleep |
| Adaptive / evolutionary | Sleep conserves energy and keeps animals safe when activity is risky | A species' sleep timing tracks its niche — predators, prey, and foraging schedules |
| Memory consolidation | Sleep sorts, strengthens, and stores the day's learning | People who sleep after studying remember more; both slow-wave and REM sleep aid memory |
- The suprachiasmatic nucleus (SCN) in the hypothalamus is the master circadian clock, reset daily by light.
- The pineal gland secretes melatonin in darkness to promote sleep; light suppresses it.
- Disrupting the clock — jet lag, shift work, late-night screens — misaligns sleep with the day.
- We sleep for restoration, adaptive safety/energy conservation, and memory consolidation.
Section 3The stages of sleep
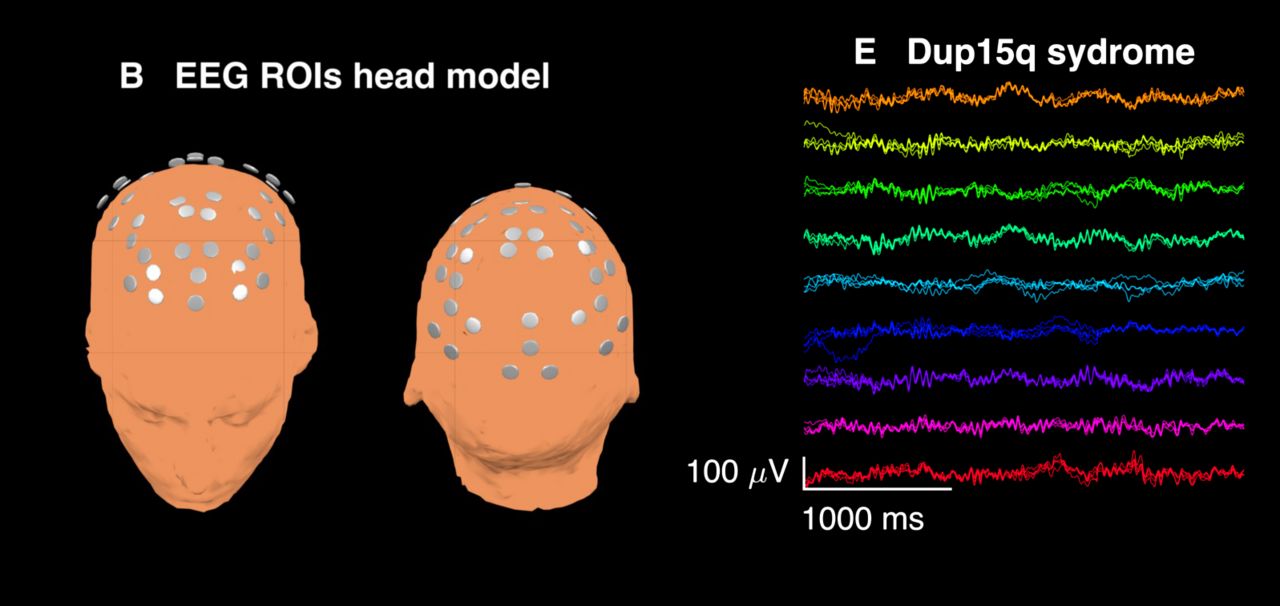
Reading sleep with the EEG
Sleep looks like nothing from the outside, but the electroencephalogram (EEG) — which records the summed electrical activity of the cortex through scalp electrodes — reveals a night of dramatic, orderly change. In wakeful alertness the EEG shows fast, low, jagged beta waves. As you close your eyes and relax, these give way to slower, more regular alpha waves. From there the brain descends through distinct stages, each with a signature wave pattern. The turning point in this science came in 1953, when Eugene Aserinsky and Nathaniel Kleitman noticed periods when a sleeper's eyes darted rapidly beneath closed lids — the discovery of REM sleep, which overturned the old assumption that sleep is a single uniform state.
The four stages: N1, N2, N3, and REM
Sleep is divided into non-REM (NREM) stages and REM. N1 is the light, drifting doorway to sleep, marked by theta waves; here you may feel a falling sensation or a sudden hypnic jerk, and if woken you might deny you were asleep at all. N2 is genuine sleep, occupying about half the night, and its EEG shows bursts called sleep spindles and sharp K-complexes thought to help protect sleep and consolidate memory. N3 is deep slow-wave sleep, dominated by large, slow delta waves; it is the hardest stage to wake from and the one most tied to physical restoration. Then comes REM, a paradox: the brain's waves look almost awake, the eyes move rapidly, vivid dreams unfold — yet the body's major muscles are paralyzed, a protective state called atonia. Because the mind is aroused while the body is switched off, REM is often called paradoxical sleep.
How sleep cycles across the night
These stages are not climbed once and left behind. A full cycle — roughly N1 → N2 → N3 → back up → REM — takes about ninety minutes, and you repeat it four to six times a night. The mix shifts as the night goes on: the early cycles are rich in deep N3 slow-wave sleep, which is why the first hours feel so restorative, while the later cycles trade deep sleep for progressively longer REM periods. The result is that most of your slow-wave sleep is banked in the first one or two cycles after you fall asleep — whenever that happens, since it is time since sleep onset that matters and not the reading on the clock — while most of your dreaming happens in the hours before you wake — which is why a cut-short night steals disproportionately from REM.
| Stage | Dominant EEG waves | What is happening |
|---|---|---|
| Awake, alert | Beta | Eyes open, active thinking and attention |
| Drowsy / relaxed | Alpha | Eyes closed, calm, on the edge of sleep |
| N1 (NREM) | Theta | Light sleep; hypnic jerks and drifting images; easily awakened |
| N2 (NREM) | Theta with sleep spindles & K-complexes | True sleep; heart rate and temperature fall; about half the night |
| N3 (NREM) | Delta (slow waves) | Deep slow-wave sleep; hardest to wake; physical repair |
| REM | Low, fast, wake-like | Vivid dreams, darting eyes, muscle atonia; "paradoxical" sleep |
- The EEG defines sleep by brain-wave shape: beta (awake), alpha (drowsy), theta (N1), spindles/K-complexes (N2), delta (N3).
- Aserinsky and Kleitman discovered REM sleep in 1953, revealing that sleep is not uniform.
- REM is "paradoxical" — wake-like brain, vivid dreams, but a paralyzed body (atonia).
- A cycle lasts ~90 minutes; early night favors deep N3, later night favors longer REM.
Section 4Dreams and sleep disorders

Theories of dreaming
Everyone dreams, several times a night, whether or not they remember it — yet why the brain generates these experiences remains debated. Sigmund Freud gave the first influential theory in The Interpretation of Dreams (1900), proposing that dreams are disguised wish fulfillment. He distinguished the manifest content — the literal storyline you remember — from the latent content, the hidden desires he believed it symbolized. Freud's specifics have found little scientific support, but the framework shaped a century of thought. A modern, biology-first rival is the activation-synthesis hypothesis of J. Allan Hobson and Robert McCarley (1977): during REM the brainstem fires more or less randomly, and the cortex, ever a meaning-maker, weaves those signals into a story — so dreams are the mind's interpretation of its own noise. A third view, the information-processing or continuity approach, treats dreaming as part of memory consolidation, replaying and sorting the concerns of waking life.
Insomnia, apnea, and narcolepsy
Sleep goes wrong for tens of millions of people, and the disorders differ sharply in mechanism. Insomnia — persistent trouble falling or staying asleep despite the chance to — is the most common complaint; the front-line treatment is not a pill but cognitive behavioral therapy for insomnia (CBT-I) and improved sleep habits. Sleep apnea is a breathing disorder: in the common obstructive form, the airway repeatedly collapses, so the sleeper stops breathing for seconds at a time, jolts partway awake to gasp, and never reaches restful deep sleep — producing loud snoring and crushing daytime fatigue. It is often treated with a CPAP machine that splints the airway open. Narcolepsy is rarer and stranger: sudden, irresistible sleep attacks in the middle of the day, frequently paired with cataplexy — a sudden loss of muscle tone triggered by strong emotion — and caused by the loss of neurons that make the wakefulness chemical hypocretin (orexin).
Parasomnias: acting out of sleep
The parasomnias are abnormal behaviors that intrude on sleep. Tellingly, sleepwalking (somnambulism) and night terrors arise from deep N3 slow-wave sleep, not from dreaming — which is why they cluster in the first third of the night and are far more common in children, who have more N3. In REM sleep behavior disorder the normal REM paralysis fails, so the sleeper physically acts out dreams, sometimes violently. Sleep paralysis is the mirror image: waking with the mind alert while REM atonia lingers, leaving you briefly unable to move — often accompanied by frightening hallucinations. Ordinary nightmares, by contrast, are simply distressing dreams that occur during REM.
| Disorder | Hallmark feature | Notes |
|---|---|---|
| Insomnia | Persistent trouble falling or staying asleep | The most common complaint; treated with sleep hygiene and CBT-I |
| Sleep apnea | Repeated pauses in breathing during sleep | Loud snoring, gasping, daytime fatigue; obstructive form treated with CPAP |
| Narcolepsy | Sudden, uncontrollable sleep attacks | Often with cataplexy; linked to loss of hypocretin/orexin neurons |
| Parasomnias | Abnormal events during sleep | Sleepwalking & night terrors arise from N3; REM behavior disorder = acting out dreams |
- Freud saw dreams as wish fulfillment (manifest vs latent content); the activation-synthesis hypothesis (Hobson & McCarley) sees them as the cortex interpreting random REM signals.
- Insomnia is trouble sleeping; first-line care is CBT-I, not medication.
- Sleep apnea = breathing pauses (CPAP); narcolepsy = sleep attacks + cataplexy (hypocretin loss).
- Parasomnias like sleepwalking and night terrors occur in deep N3, not REM.
Section 5Psychoactive drugs
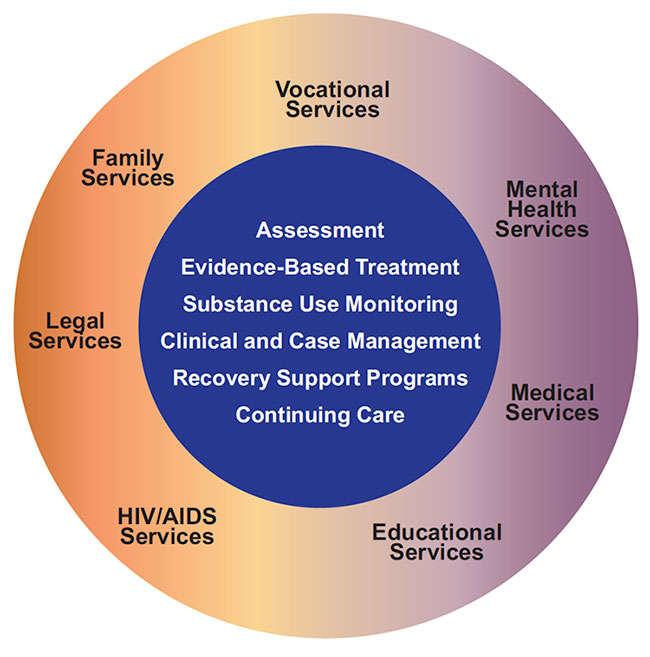
How drugs reach the mind
A psychoactive drug is any chemical that changes perception, mood, thinking, or behavior by altering activity at the synapse — mimicking a neurotransmitter, blocking its receptor, or changing how much is released or reabsorbed. Many drugs of abuse converge on one target: the brain's reward pathway, a dopamine circuit running from the ventral tegmental area to the nucleus accumbens that normally reinforces survival behaviors like eating. By flooding this circuit with dopamine, drugs teach the brain to want them — the neural root of craving. Psychoactive drugs sort into four broad families by what they do to the central nervous system.
The four families: depressants, stimulants, opioids, hallucinogens
Depressants slow the central nervous system, largely by boosting the inhibitory neurotransmitter GABA. Alcohol, barbiturates, and benzodiazepines belong here; in small doses they relax and reduce anxiety, but they impair coordination and judgment and, in overdose, can suppress breathing to the point of death. Stimulants do the opposite, speeding the nervous system and raising dopamine and norepinephrine: caffeine, nicotine, cocaine, amphetamines, and MDMA produce alertness and euphoria along with a racing heart and, often, a hard crash. Opioids — morphine, codeine, heroin, oxycodone, and the highly potent fentanyl — bind the body's own endorphin receptors, delivering powerful pain relief and euphoria while dangerously depressing breathing. Hallucinogens such as LSD, psilocybin, and mescaline distort perception and sensation, sometimes producing vivid imagery or a sense of altered reality; LSD works chiefly by acting on serotonin receptors.
Tolerance, dependence, and addiction
Repeated use changes the brain. Tolerance is a diminishing response to the same dose — the nervous system adapts, so larger amounts are needed to reach the original effect, a slide that pushes users toward dangerous quantities. Dependence comes in two forms. Physical dependence means the body has adjusted to the drug and produces a withdrawal syndrome — sometimes severe — when it is stopped. Psychological dependence is the emotional pull: the craving and compulsive seeking that can persist long after the body has detoxed. When drug use becomes compulsive and continues despite clear harm, clinicians call it a substance use disorder (addiction) — understood today as a chronic, treatable brain condition rather than a simple failure of willpower.
| Family | Examples | Effect on the nervous system |
|---|---|---|
| Depressants | Alcohol, barbiturates, benzodiazepines | Slow the CNS (enhance GABA); relaxation, sedation, impaired coordination; overdose stops breathing |
| Stimulants | Caffeine, nicotine, cocaine, amphetamines, MDMA | Speed the CNS (raise dopamine/norepinephrine); alertness, euphoria, higher heart rate, crash |
| Opioids | Morphine, codeine, heroin, oxycodone, fentanyl | Bind endorphin receptors; powerful pain relief and euphoria; dangerous respiratory depression |
| Hallucinogens | LSD, psilocybin, mescaline, PCP | Distort perception and sensation; LSD acts on serotonin receptors |
- A psychoactive drug alters mood, perception, or awareness by changing synaptic activity, often hijacking the dopamine reward pathway.
- The four families are depressants (slow CNS), stimulants (speed CNS), opioids (endorphin receptors), and hallucinogens (distort perception).
- Tolerance = needing more for the same effect; dependence = physical withdrawal plus psychological craving.
- Mixing depressants (opioids + alcohol) multiplies respiratory depression; naloxone reverses opioid overdose.
The chapter in one breath
- Consciousness is awareness of internal and external stimuli, and it runs along a continuum from focused attention to automatic processing to sleep.
- Biological rhythms — circadian (~24 h), ultradian, infradian — drive the daily rise and fall of alertness and sleep.
- The SCN in the hypothalamus is the master clock, reset by light; it drives melatonin release from the pineal gland to time sleep.
- We sleep for restoration, evolutionary safety, and memory consolidation.
- Sleep moves through NREM stages N1–N3 and REM, defined by EEG waves; cycles last ~90 minutes, with deep sleep early and REM late.
- Dreams are explained by Freud's wish fulfillment and the activation-synthesis hypothesis; disorders include insomnia, apnea, narcolepsy, and parasomnias.
- Psychoactive drugs — depressants, stimulants, opioids, hallucinogens — alter the brain and can produce tolerance and dependence.
ReferenceWords worth knowing
A quick reference for the terms in this chapter — skim it now, or circle back whenever a word trips you up.
- Activation-synthesis hypothesis
- The theory that dreams are the cortex's attempt to make sense of random neural signals generated in the brainstem during REM sleep.
- Cataplexy
- A sudden loss of muscle tone, often triggered by strong emotion, that is a hallmark of narcolepsy.
- Circadian rhythm
- A biological cycle of roughly 24 hours, such as the sleep–wake cycle, governed by the body's internal clock.
- Consciousness
- Awareness of internal states and of the external environment.
- Dependence
- A state in which the body or mind has adapted to a drug, producing withdrawal (physical) or craving (psychological) when it is stopped.
- Depressant
- A drug that slows central nervous system activity, such as alcohol or a benzodiazepine.
- Hallucinogen
- A drug that distorts perception and sensory experience, such as LSD or psilocybin.
- Insomnia
- Persistent difficulty falling asleep or staying asleep despite adequate opportunity.
- Latent content
- In Freud's theory, the hidden, symbolic meaning beneath a dream's storyline.
- Manifest content
- In Freud's theory, the literal storyline of a dream as it is remembered.
- Melatonin
- A hormone released by the pineal gland in darkness that promotes sleepiness.
- Narcolepsy
- A disorder marked by sudden, uncontrollable sleep attacks, often accompanied by cataplexy.
- NREM sleep
- Non-rapid-eye-movement sleep, comprising the stages N1, N2, and N3.
- Opioid
- A drug that binds the body's endorphin receptors to relieve pain and produce euphoria, such as morphine or heroin.
- Parasomnia
- An abnormal behavior or event during sleep, such as sleepwalking or night terrors.
- Psychoactive drug
- A chemical that changes perception, mood, or consciousness by altering brain chemistry.
- REM sleep
- Rapid-eye-movement sleep, marked by wake-like brain waves, vivid dreams, and muscle paralysis (atonia).
- Sleep apnea
- A disorder in which breathing repeatedly stops and restarts during sleep.
- Stimulant
- A drug that speeds up central nervous system activity, such as caffeine or cocaine.
- Suprachiasmatic nucleus (SCN)
- A region of the hypothalamus that serves as the body's master circadian clock.
- Tolerance
- A reduced response to a drug over time, so that larger doses are needed for the same effect.
- Withdrawal
- Unpleasant physical and psychological symptoms that appear when a dependent person stops using a drug.