Immune Disorders
The immune system is the body's best guard. When it misfires, it turns into one of the body's worst threats. Sometimes it overreacts to something harmless, like pollen or a dose of penicillin, and the response itself does the damage. Sometimes it turns on the body's own tissues. Sometimes it is too weak to defend at all. And sometimes blood or an organ is given on purpose to help, and the immune system attacks that help. This chapter walks through all of those problems. Hypersensitivity. Allergy and anaphylaxis. Autoimmunity. Immunodeficiency. Transfusion and transplant reactions. For each one you will see what it looks like in a real person, and what keeps that person safe.
By the end of this chapter you can
- Say what hypersensitivity is. Then tell the four types (I to IV) apart by mediator, timing, and mechanism.
- Explain type I allergy from sensitization through IgE, mast-cell degranulation, and anaphylaxis.
- Say why epinephrine is the first-line treatment for anaphylaxis, and spot the emergency.
- Explain how self-tolerance breaks down. Then name common autoimmune diseases and their targets.
- Tell primary (congenital) from secondary (acquired) immunodeficiency.
- Walk through the course of HIV/AIDS using CD4 counts and opportunistic infections.
- Explain ABO and Rh blood typing, and the cause of a hemolytic transfusion reaction.
- Tell the major kinds of graft apart. Then describe rejection and graft-versus-host disease.
Section 1Hypersensitivity: when defense becomes damage
An immune response that harms the host
A healthy immune response protects you. It clears an invader, then it quiets down. A hypersensitivity reaction is not like that. It is an immune response that runs too strong, aims at the wrong thing, or is simply not needed. The response itself injures the body's own tissues. The trigger can be truly dangerous, such as a microbe. It can be harmless, such as pollen, a food, or a drug. It can even be part of the body itself. All hypersensitivities share one feature. The damage comes from the immune system's own activity, not straight from the trigger.
Almost every hypersensitivity needs a first, quiet exposure called sensitization. That first meeting causes no symptoms. The immune system just learns the antigen and builds a stock of antibodies or primed T cells against it. The big reaction comes on a later exposure, when that stock fires. So a drug can go in with no trouble the first time, then cause a violent reaction the second time. "No reaction last time" never means a drug is safe.
The four types (Gell and Coombs)
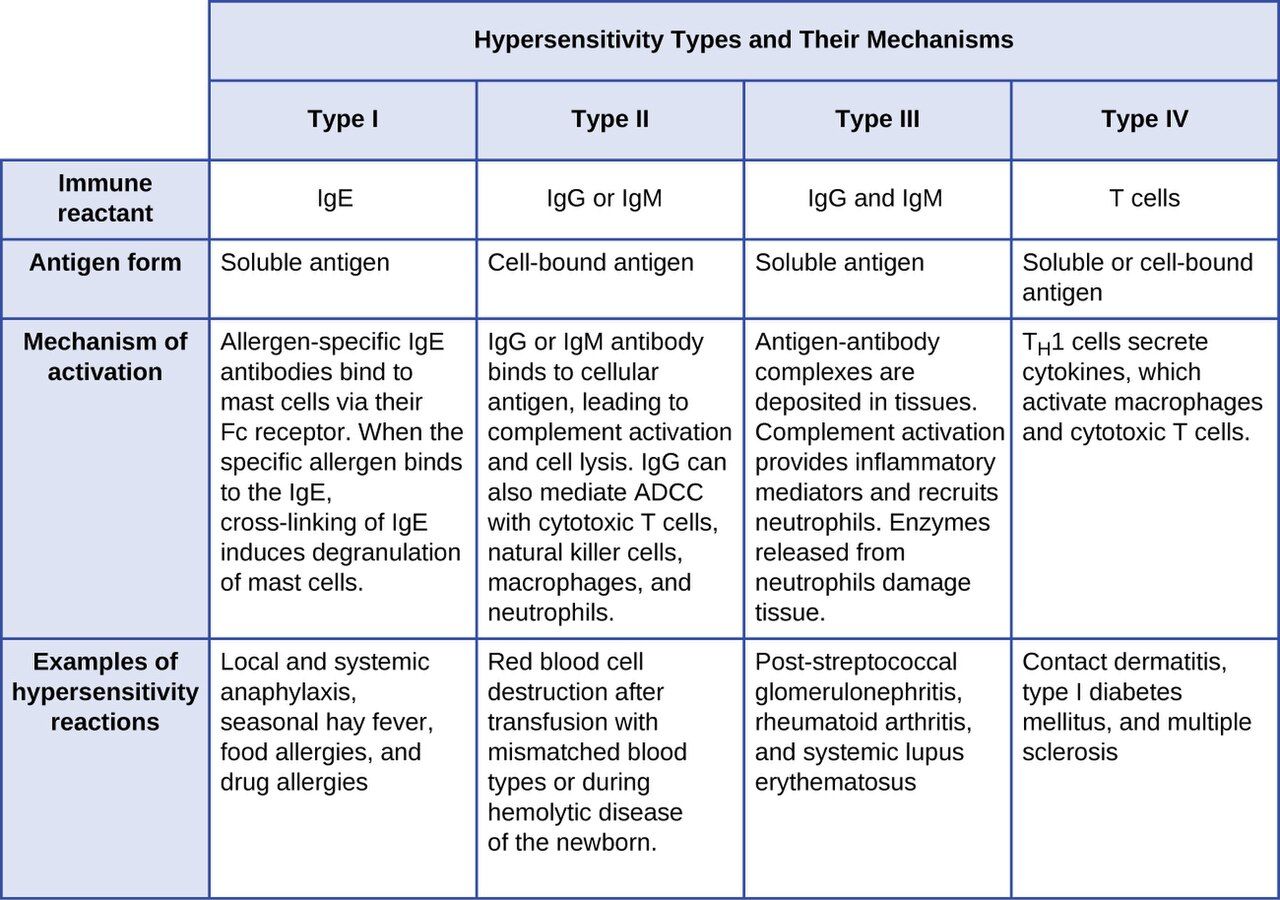
In the 1960s, Gell and Coombs sorted hypersensitivities into four types. They sorted them by the immune mechanism behind each one. The first three run on antibodies. The fourth runs on T cells. A handy memory aid is ACID. Type I is Anaphylactic, or allergic. Type II is Cytotoxic. Type III is Immune-complex. Type IV is Delayed. Types I to III strike within minutes to hours, because the antibodies are already in place. Type IV takes a day or more, because T cells have to be called to the site.
| Type | Also called | Mediator | Timing | Mechanism & example |
|---|---|---|---|---|
| I | Immediate / allergic / anaphylactic | IgE on mast cells | Seconds to minutes | Allergen cross-links IgE → mast-cell degranulation. Hay fever, food allergy, anaphylaxis |
| II | Cytotoxic | IgG / IgM vs. cell-surface antigen | Minutes to hours | Antibody binds a cell, marking it for destruction (complement, phagocytes). Hemolytic transfusion reaction, HDN, autoimmune hemolytic anemia |
| III | Immune-complex | IgG in antigen–antibody complexes | Hours | Soluble complexes deposit in vessels, joints, kidneys and inflame them. Serum sickness, SLE, some glomerulonephritis |
| IV | Delayed-type / cell-mediated | T cells (no antibody) | 1–3 days | Sensitized T cells release cytokines, recruit macrophages. Contact dermatitis (poison ivy, nickel), TB skin test |
Keep the antibody-versus-T-cell split in mind. It explains the speed you see. If someone breaks out in hives within minutes of a bee sting, you are watching type I. If a rash shows up two days after a new skin cream, that slow start points to type IV. Timing is a real clue, not a trivia item.
Where all four show up
Each type maps to a real event. Type I is the drug allergy and the anaphylaxis that has to be treated in seconds. Type II is the mismatched blood transfusion that has to be prevented. Type III sits under lupus flares, and under the joint and kidney damage of immune-complex disease. Type IV is the positive tuberculin skin test that gets read at 48 to 72 hours. It is also the contact dermatitis someone blames on gloves or tape.
- Hypersensitivity is an immune response that damages the host's own tissues.
- Most reactions need a quiet sensitization exposure first. The reaction fires on a later exposure.
- Types I to III are antibody-mediated and fast. Type IV is T-cell-mediated and delayed 1 to 3 days.
- Remember ACID: Anaphylactic, Cytotoxic, Immune-complex, Delayed.
Section 2Allergy and anaphylaxis
Sensitization first, reaction later
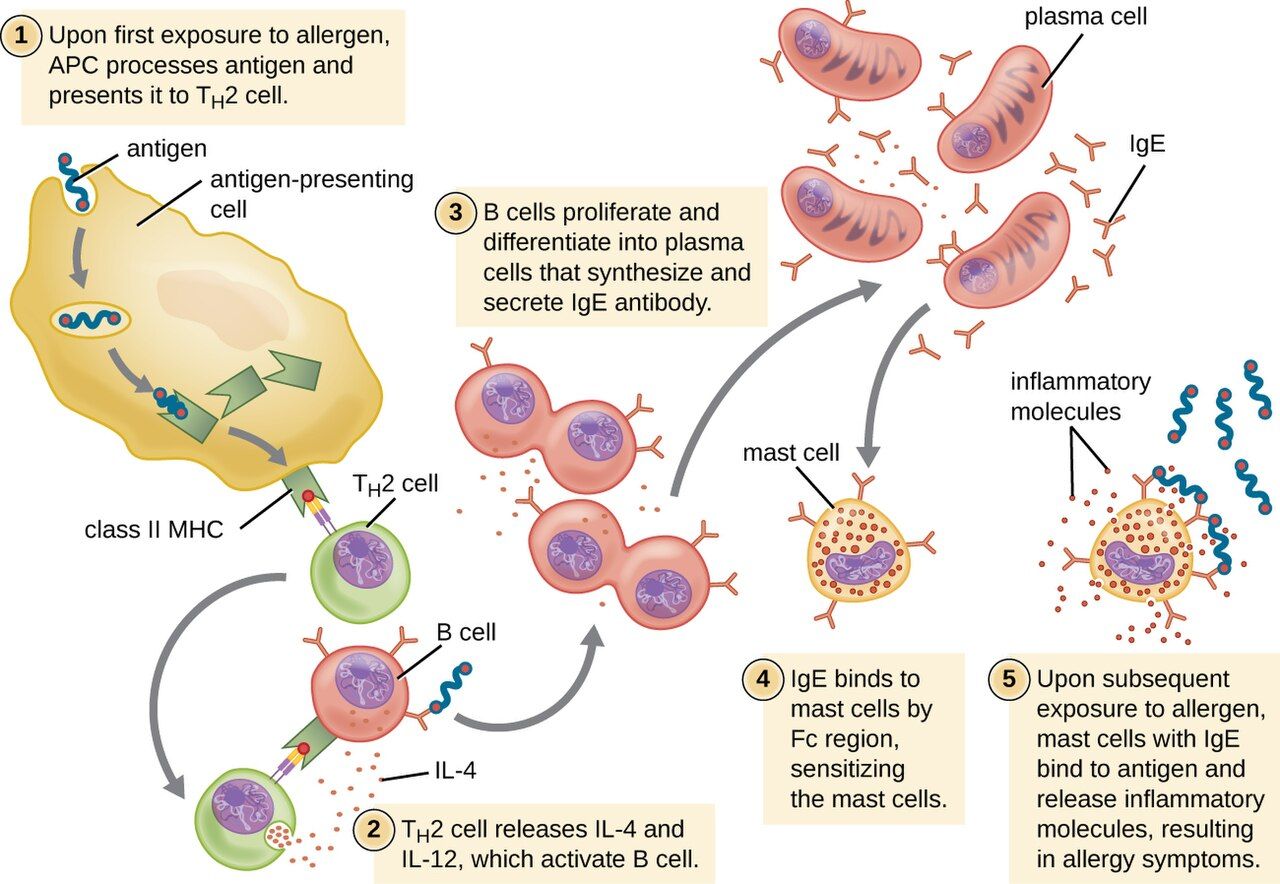
A type I reaction is what most people mean by "an allergy." It runs in two acts. In sensitization, a first exposure to a harmless allergen is taken up and shown to the immune system. The allergen might be pollen, peanut, penicillin, or bee venom. The immune system answers by making IgE antibody against that one allergen. The IgE then coats mast cells in the tissues and basophils in the blood. Those cells are now armed. Nothing dramatic happens yet. The person feels fine.
On the next exposure, the allergen bridges two IgE molecules sitting side by side on a mast cell. That bridging is cross-linking, and it is the trigger. Within seconds the mast cell goes through degranulation. It dumps stored histamine and other mediators, and it starts building leukotrienes and prostaglandins. Those mediators cause the whole familiar package. Vessels widen, so you see redness, warmth, and falling blood pressure. Vessels leak, so you see swelling and hives. Smooth muscle squeezes, so you get bronchospasm and cramping. Glands pour out fluid, so you get a runny nose and watery eyes.
From a local nuisance to a whole-body emergency
Where the reaction happens decides how serious it is. A localized reaction stays near the point of contact. That is allergic rhinitis (hay fever), hives on one patch of skin, or asthma in the airways. A systemic reaction is anaphylaxis. Mediators pour out body-wide, usually because the allergen got into the bloodstream. An injected drug, an IV contrast agent, a sting, or a swallowed food can all do that. Anaphylaxis is a life-threatening emergency. Vessels widen everywhere, so blood pressure crashes, and that is distributive shock. At the same time the airway swells and the bronchi clamp down, which can shut off breathing within minutes.
| Feature | Localized allergy | Anaphylaxis (systemic) |
|---|---|---|
| Where mediators act | Near contact site | Whole body |
| Typical signs | Hives, itching, sneezing, wheeze | Hives plus hypotension, throat/airway swelling, stridor, wheeze, GI cramps, sense of doom |
| Main danger | Discomfort | Airway closure and shock — can kill in minutes |
| First-line treatment | Antihistamine; avoid trigger | Epinephrine, IM, immediately |
Spotting and treating the emergency
The drug that reverses anaphylaxis is epinephrine. It goes intramuscularly into the outer thigh, and it has to be given at the first sign. Not after antihistamines. Not after a wait-and-see. Epinephrine squeezes blood vessels to bring blood pressure back up. It relaxes airway muscle to open breathing. It also calms mast cells. Antihistamines and corticosteroids help alongside it, but they are far too slow and far too weak to carry the job alone. With the drug, protect the airway and give oxygen. Lay the person flat with the legs raised, unless breathing is easier sitting up. Run IV fluids for the shock. Then watch closely, because a biphasic reaction can return hours later, even after everything looks fine.
Prevention counts just as much. A known allergy has to be checked, banded, and honored at every dose of medicine. The most common cause of a preventable drug reaction is an allergy history that was missed or ignored. Anyone with a severe allergy needs to learn to use an epinephrine auto-injector. They also need to know to call emergency services and go to the hospital even after using it.
- Type I allergy is sensitization first. The body makes IgE and arms mast cells. The reaction comes later, when allergen cross-links IgE.
- Mast-cell degranulation releases histamine. That brings vasodilation, swelling, bronchospasm, and secretions.
- Anaphylaxis is type I gone body-wide. Airway swelling and distributive shock can be fatal in minutes.
- Treat anaphylaxis with IM epinephrine right away. Then watch for a biphasic return.
Section 3Autoimmunity: the body against itself
How self-tolerance breaks down
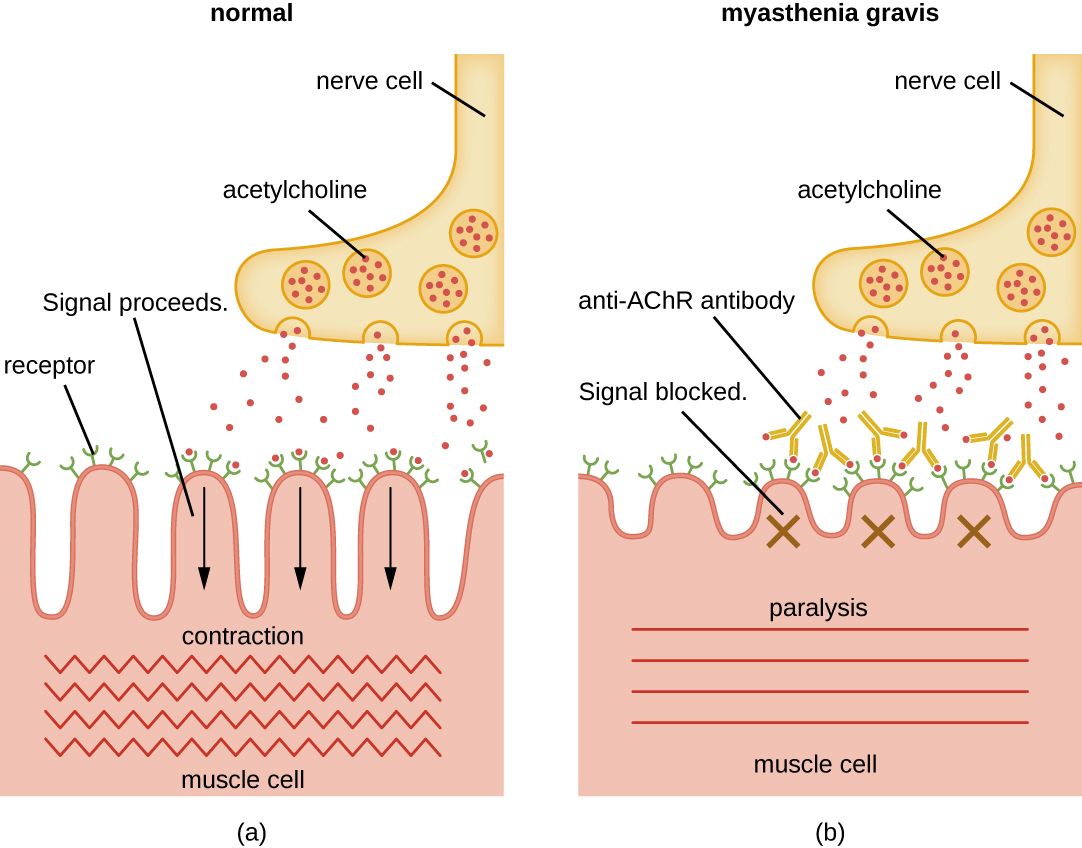
Early in life, the immune system learns to leave the body's own molecules alone. That state is called self-tolerance. Young lymphocytes that react too strongly against self get deleted or shut off before they mature. Autoimmunity is the failure of that screening. Self-reactive T cells, or antibodies called autoantibodies, slip past the controls and attack the body's own tissues. The result is an autoimmune disease. The attack uses the same weapons as any hypersensitivity. Often it is type II, with autoantibodies against targets on a cell surface. Sometimes it is type III, with immune complexes. Sometimes it is type IV, with self-reactive T cells.
Why tolerance fails is usually a mix of things. A genetic risk sets the stage. Many autoimmune diseases run in families and link to certain HLA/MHC types. Then something in the environment pulls the trigger, and that something is often an infection. One well-studied route is molecular mimicry. A microbial antigen looks so much like a human protein that antibodies made against the microbe attack the body too. The classic case is rheumatic fever. Antibodies raised against Streptococcus pyogenes cross-react with heart tissue. Autoimmune diseases also fall more often on women. Many come and go in flares and remissions.
Organ-specific versus systemic disease
It helps to sort these diseases by how much of the body they hit. Organ-specific diseases aim autoantibodies or T cells at a single tissue. The thyroid. The pancreatic islets. The neuromuscular junction. The damage and the symptoms stay focused. Systemic diseases, such as systemic lupus erythematosus, make autoantibodies against parts found all over the body, such as the cell nucleus. So they injure many organs at once. Skin, joints, kidneys, blood, and heart.
| Disease | Target | Effect | Scope |
|---|---|---|---|
| Graves’ disease | TSH receptor (stimulating antibody) | Overactive thyroid (hyperthyroidism) | Organ-specific |
| Hashimoto thyroiditis | Thyroid tissue | Underactive thyroid (hypothyroidism) | Organ-specific |
| Type 1 diabetes mellitus | Pancreatic islet β-cells | No insulin production | Organ-specific |
| Myasthenia gravis | Acetylcholine receptor | Muscle weakness, ptosis | Organ-specific |
| Multiple sclerosis | CNS myelin sheath | Nerve conduction failure | Organ-specific (CNS) |
| Rheumatoid arthritis | Joint synovium | Symmetric joint inflammation, deformity | Systemic |
| Systemic lupus erythematosus | Nuclear antigens (anti-nuclear antibodies) | Skin, joints, kidney, blood, heart | Systemic |
Living with an autoimmune disease
Most autoimmune diseases have no cure. So care aims to hold back the immune attack and manage what it has already damaged. Treatment leans on immunosuppression. That means corticosteroids and other drugs that quiet the immune response. It brings its own hazard. Someone who is deliberately immunosuppressed is also more open to infection, which blurs the line between an autoimmune problem and an immunodeficiency one. Some organ-specific diseases are handled another way. Instead of suppressing anything, you simply replace what was lost. Insulin does that in type 1 diabetes. Thyroid hormone does it in Hashimoto disease.
- Autoimmunity is a loss of self-tolerance. Autoantibodies or self-reactive T cells attack the body.
- Causes combine genetic risk with an environmental trigger. Molecular mimicry, as in rheumatic fever, is one route.
- Diseases are organ-specific (Graves, Hashimoto, type 1 diabetes, myasthenia gravis, MS) or systemic (RA, SLE).
- Care centers on immunosuppression or hormone replacement. Immunosuppression raises infection risk.
Section 4Immunodeficiency and HIV/AIDS
When defenses are too weak
Hypersensitivity and autoimmunity are the immune system doing too much. Immunodeficiency is it doing too little. Some part of the immune system is missing or not working. So infections that a healthy body would shrug off cannot be cleared. Worse, opportunistic organisms move in. Those are microbes that rarely trouble anyone with a working immune system. Immunodeficiencies split into two groups by where they come from.
Primary immunodeficiencies are congenital. The person is born with a genetic defect in some part of immunity. They run from mild to catastrophic. Selective IgA deficiency is often silent and causes no trouble at all. The most severe is severe combined immunodeficiency (SCID). In SCID, both B cells and T cells are missing or do not work. An affected infant has almost no defense. Without treatment such as a bone-marrow transplant, they do not survive infancy. That is where the "bubble" isolation once used to protect them came from.
Secondary (acquired) immunodeficiencies are far more common. They build up after birth from some outside cause. Malnutrition is the leading cause worldwide. Certain cancers do it too, above all the leukemias and lymphomas. So do chemotherapy and other immunosuppressive drugs, radiation, aging, and viral infection. The most important virus here is HIV. Many people are secondarily immunodeficient because of their own treatment. Anyone on chemotherapy, high-dose steroids, or anti-rejection drugs is in that group.
| Feature | Primary immunodeficiency | Secondary immunodeficiency |
|---|---|---|
| Origin | Congenital (genetic) | Acquired after birth |
| Onset | Usually infancy/childhood | Any age |
| Examples | SCID, selective IgA deficiency, DiGeorge syndrome | HIV/AIDS, malnutrition, chemotherapy, leukemia, steroids |
| Frequency | Rare | Common — a large share of people in hospital |
HIV and AIDS
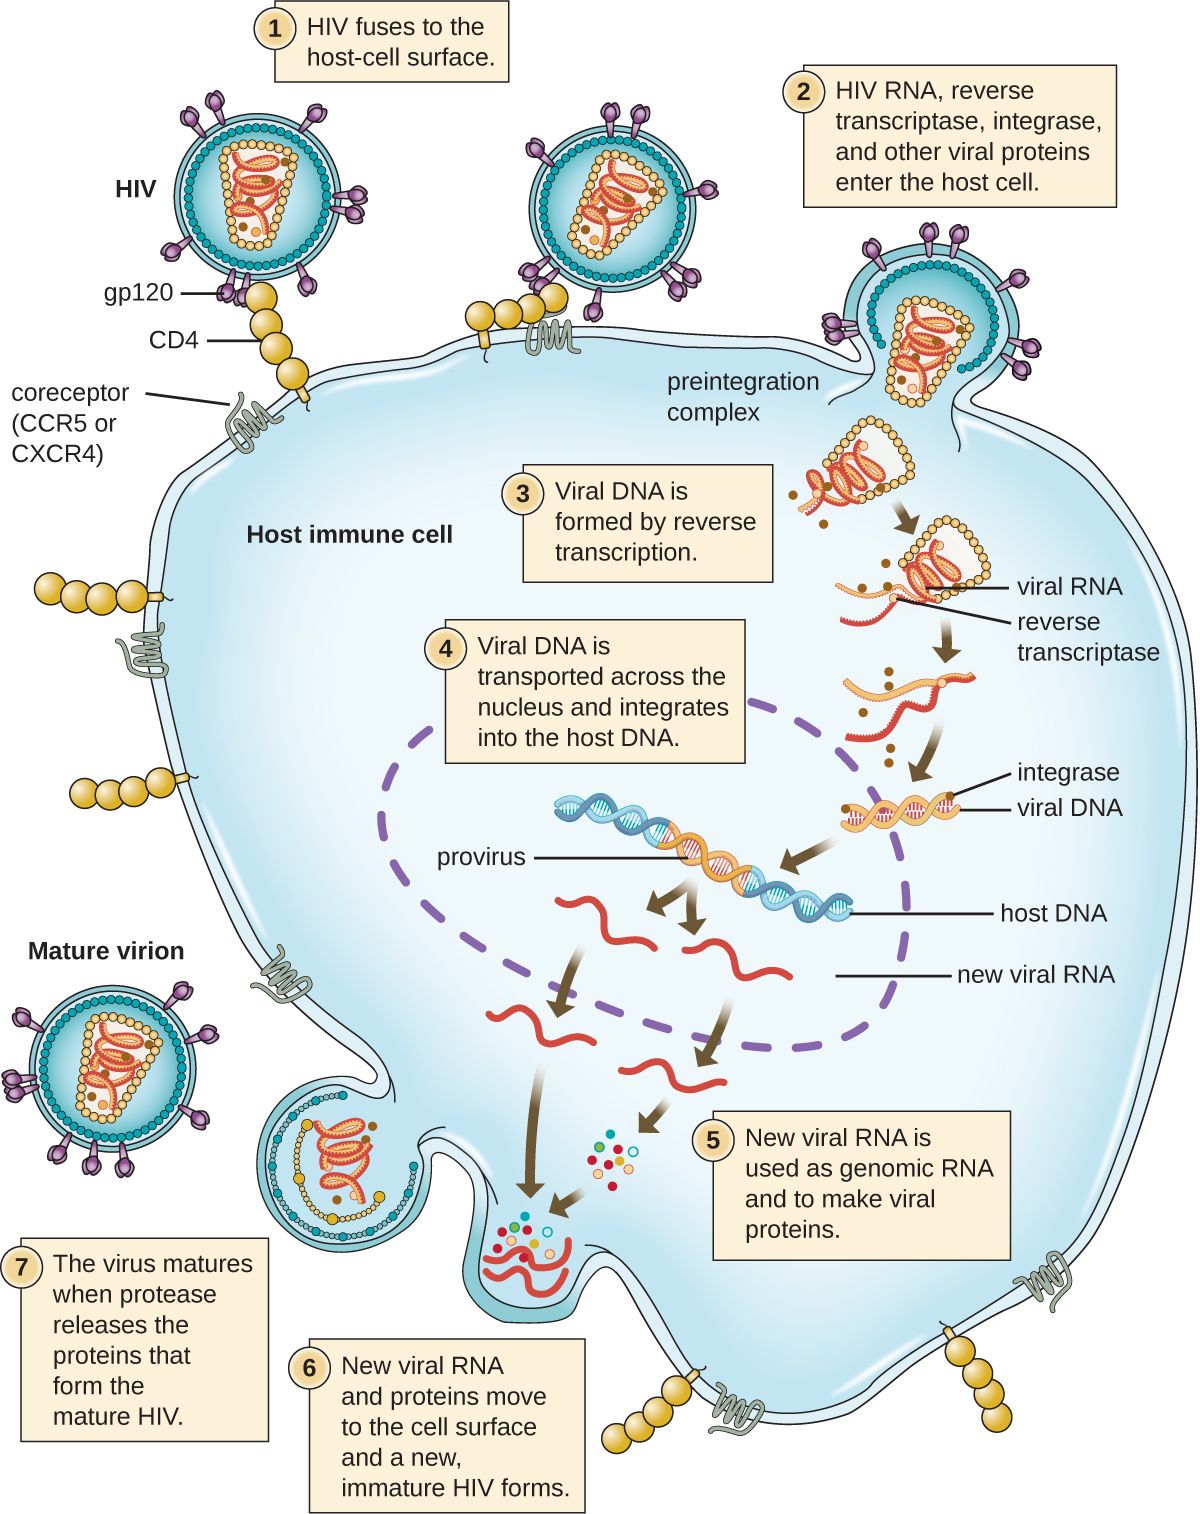
The human immunodeficiency virus (HIV) is a retrovirus. It targets the one cell that coordinates the whole immune response, the CD4 helper T cell. Over years, HIV infects and destroys those cells. As the CD4 count falls, the immune system loses its conductor, and fighting off infection gets harder and harder. HIV spreads through blood, through sexual contact, and from mother to child in pregnancy, at birth, or through breastfeeding. It does not spread through casual contact.
AIDS stands for acquired immunodeficiency syndrome. It is the advanced stage of HIV infection, and it is defined two ways. Either the CD4 count drops below 200 cells/µL, where normal is roughly 500 to 1,500. Or an AIDS-defining opportunistic illness appears. Those are infections and cancers that a working immune system holds back. The list takes in Pneumocystis jirovecii pneumonia, Candida of the esophagus, widespread tuberculosis, cytomegalovirus, and Kaposi sarcoma. The lower the CD4 count, the wider the range of opportunists that can take hold.
The story is far more hopeful than it once was. Antiretroviral therapy (ART) uses combinations of drugs that block different steps of the viral life cycle. ART can push HIV down to undetectable levels. It protects the CD4 count, stops the slide into AIDS, and makes the virus untransmittable through sex. For many people, HIV is now a long-term condition that can be managed. What matters most is support for adherence to a lifelong drug routine, a close watch for opportunistic infections, and steady use of standard precautions. Those are the same barrier practices that guard against every bloodborne pathogen.
- Immunodeficiency is too little immune function. It opens the door to opportunistic infections.
- Primary means congenital, as in SCID. Secondary means acquired, as in HIV, malnutrition, chemotherapy, or steroids, and it is far more common.
- HIV destroys CD4 helper T cells. AIDS means CD4 under 200 cells/µL, or an AIDS-defining opportunistic illness.
- ART suppresses HIV and protects immunity. Support for adherence and standard precautions go with it.
Section 5Transfusion and transplant reactions
ABO and Rh: the blood you can safely give
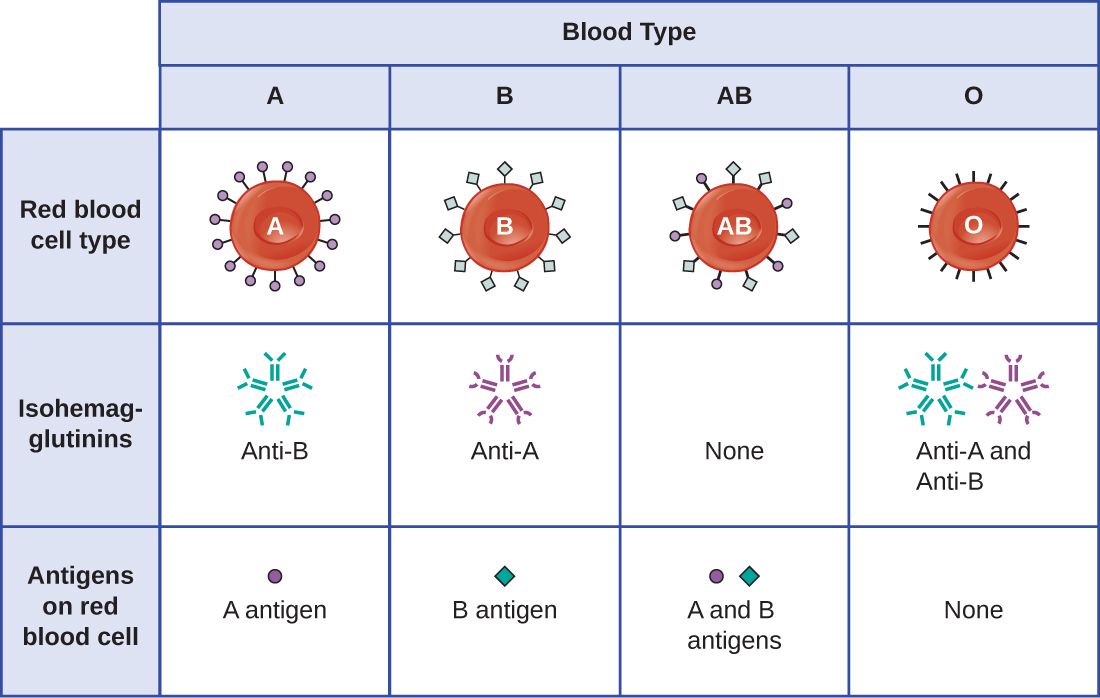
Red blood cells carry surface molecules that the immune system reads as antigens. The most important set is the ABO system. Type A cells carry the A antigen. Type B carry B. Type AB carry both. Type O carry neither. Here is the part that matters. Each person naturally makes antibodies against the ABO antigen they lack. A type A person has anti-B antibodies. A type O person has both anti-A and anti-B. That is why blood has to be matched. Transfuse the wrong ABO type and the recipient's antibody attacks the donor red cells, and those cells are destroyed.
A second system, Rh, adds "positive" or "negative." Rh-positive cells carry the D antigen. Rh-negative cells do not. Anti-Rh antibodies behave differently from the ABO ones. They are not present from birth. An Rh-negative person makes them only after being exposed to Rh-positive blood. Type O-negative red cells carry none of these antigens, so O-negative is the emergency universal donor for red cells. Type AB-positive plasma carries no anti-A and no anti-B, so AB-positive is the universal recipient.
| Blood type | Antigens on red cells | Antibodies in plasma | Can receive red cells from |
|---|---|---|---|
| A | A | anti-B | A, O |
| B | B | anti-A | B, O |
| AB | A and B | none | A, B, AB, O (universal recipient) |
| O | none | anti-A and anti-B | O only (universal donor) |
When a transfusion goes wrong
An acute hemolytic transfusion reaction is a type II hypersensitivity and a true emergency. It is almost always caused by an ABO mismatch, and that mismatch usually traces back to a clerical or identification error at the bedside. The recipient's antibodies bind the transfused donor cells and destroy them, which is hemolysis. That brings fever, chills, flank or back pain, dark urine, and low blood pressure. It can go on to kidney failure and death. The response has to be instant. Stop the transfusion. Keep the IV line open with saline. Notify the provider and the blood bank. Because these reactions start with mistaken identity, the two-person check of the person and the unit at the bedside is not paperwork. It is the actual guard against a fatal error.
A related problem crosses the placenta. Hemolytic disease of the newborn (HDN) happens when an Rh-negative mother was sensitized to Rh-positive blood in an earlier pregnancy. She makes anti-Rh antibodies. Those antibodies cross into a later Rh-positive fetus and destroy its red cells. It is largely preventable. Giving Rh immune globulin (RhoGAM) to Rh-negative mothers stops the sensitization from ever happening.
Transplants and rejection
Transplanting tissue raises the same problem in a new form. The recipient's immune system reads donor cells as foreign, chiefly by their MHC/HLA molecules, and attacks the graft. How hard it attacks depends on how closely donor and recipient are matched. An autograft moves tissue from one spot on a body to another spot on the same body, as in a skin graft. An isograft goes between identical twins. Neither one is rejected. An allograft goes between two genetically different people of the same species, which is the usual organ transplant. It is rejected unless the immune response is suppressed. A xenograft goes between species, and it faces the strongest rejection of all.
Rejection comes in three tempos. Hyperacute rejection hits within minutes, driven by antibodies that were already there. Acute rejection takes days to weeks and is run by T cells. Chronic rejection takes months to years. To keep an allograft alive, the recipient takes immunosuppressant drugs for life. As always, that trades rejection risk for infection risk. One more danger runs the other way. In a bone-marrow or stem-cell transplant, the immune cells in the graft can attack the recipient's body. That is graft-versus-host disease (GVHD).
- ABO works on one rule. You make antibodies against the antigen you lack. O-negative is the universal red-cell donor, and AB-positive the universal recipient.
- An acute hemolytic transfusion reaction is a type II reaction from an ABO mismatch. Stop the transfusion at once.
- HDN comes from Rh incompatibility, and Rh immune globulin prevents it.
- Grafts: an autograft or isograft is not rejected, and an allograft needs immunosuppression. GVHD is the graft attacking the host.
The chapter in one breath
- Hypersensitivity is an immune response that harms the host. The four types differ by mediator and timing. Types I to III use antibody, and type IV uses T cells.
- Type I allergy runs from sensitization and IgE to mast-cell degranulation. Body-wide release is anaphylaxis, treated with IM epinephrine right away.
- Autoimmunity is lost self-tolerance. It is either organ-specific, as in Graves, type 1 diabetes, and myasthenia gravis, or systemic, as in RA and SLE.
- Immunodeficiency is too little immunity. Primary is congenital, such as SCID. Secondary is acquired, such as HIV, chemotherapy, or malnutrition.
- HIV destroys CD4 T cells. AIDS means CD4 under 200/µL or an opportunistic illness, and ART controls it.
- ABO/Rh matching prevents the type II hemolytic transfusion reaction. Identification errors are the cause, so the bedside check is the safeguard.
- Grafts are rejected by how badly they are mismatched. Allografts need lifelong immunosuppression, and GVHD is the graft attacking the host.
ReferenceWords worth knowing
A quick reference for the terms in this chapter. Skim it now, or come back whenever a word trips you up.
- Allergen
- An otherwise harmless antigen that sets off a type I (allergic) hypersensitivity response.
- Allograft
- A transplant between two genetically different people of the same species. It is the usual organ transplant, and it needs immunosuppression.
- Anaphylaxis
- A severe, body-wide type I reaction with airway swelling and distributive shock. It is a life-threatening emergency treated with epinephrine.
- Autoantibody
- An antibody aimed at the body's own tissues.
- Autoimmunity
- A failure of self-tolerance in which the immune system attacks the body's own cells and tissues.
- CD4 helper T cell
- The lymphocyte that coordinates the immune response, and the main target of HIV.
- Graft-versus-host disease (GVHD)
- A reaction in which transplanted (graft) immune cells attack the recipient's tissues. It is seen with bone-marrow and stem-cell transplants.
- Hemolytic disease of the newborn (HDN)
- Destruction of a fetus's red cells by maternal anti-Rh antibodies. Rh immune globulin prevents it.
- Hemolytic transfusion reaction
- A type II reaction from an ABO-mismatched transfusion. The recipient's antibodies destroy the donor red cells.
- Hypersensitivity
- An exaggerated or misdirected immune response that damages the host's own tissues.
- IgE
- The antibody class that arms mast cells and basophils and drives type I hypersensitivity.
- Immunodeficiency
- A weak immune response. It is either primary (congenital) or secondary (acquired).
- Mast cell
- A tissue cell coated with IgE. It releases histamine and other mediators when it degranulates.
- Molecular mimicry
- A microbial antigen that looks like a self-protein, so anti-microbe antibodies attack the body too. Rheumatic fever is the classic example.
- Opportunistic infection
- An infection by a normally harmless microbe that takes hold once host defenses are weakened.
- Primary immunodeficiency
- A congenital, gene-based defect in immune function, such as SCID.
- Rh factor
- The D red-cell antigen. Rh-positive cells carry it, and Rh-negative cells do not.
- Secondary immunodeficiency
- An acquired loss of immune function from an outside cause, such as HIV, malnutrition, drugs, or cancer.
- Self-tolerance
- The immune system's normal ability to recognize the body's own molecules and leave them alone.
- Sensitization
- The quiet first exposure in which the immune system builds antibodies or primed cells against an antigen, setting up a later reaction.
- Severe combined immunodeficiency (SCID)
- A severe primary immunodeficiency with no working B cells and no working T cells.